Healthcare Pharma & Life Sciences Other Industries
All Services Performance Marketing ChatGPT Ads India · NEW Social Media Marketing SEO & AEO / LLM YouTube Marketing LLM Optimization Brand & Growth Consulting AI Solutions Industries We Serve
Enterprise Hub · All Solutions + Services Growth Transformation AI Transformation Revenue Operations Fractional CGO Growth Operating System Executive Growth Advisory
Clinic Launch Programme (Hub) NABH Consulting India Healthcare Brand Launch Clinic SOP Creation Logo Design (Healthcare) Brand Book Creation Clinic Launch Marketing D2C Brand Launch Clinic Interior Design
Workforce Hub For Employers — post a requirement For Professionals — register Public Openings Training Academy AI Training Flagship
Hawk · CRM Intelligence (NEW) YODA · YouTube Intelligence Angryturtle · GBP Intelligence (NEW) Prism Pulse · Instagram Analytics (NEW) Beacon · Attribution Agency OS · Dashboards Phoenix · Clinic Revenue HealthPro 360 · PMS/HMS AI Patient Lifecycle Bots AI Lead Management System Smart Appointment System Healthcare CRM Patient Feedback System AI, Analytics & Automation Digital Transformation Calculators Free Digital Health Audit →
All 13 calculators → 🎯 Business Exploration Matrix (New) Dental Clinic Setup IVF Clinic + Lab Setup Multi-Specialty Hospital Setup Aesthetic / Cosmetology Clinic Dermatology Clinic Setup Generic Clinic Setup Physiotherapy Clinic Setup Diagnostic Centre Setup CAC Calculator CPQL Calculator Franchise ROI Calculator Revenue Leakage Calculator CRM ROI Calculator
All Events Workshop 1 · Jun 13 · AI in Clinical Practice Workshop 2 · Jun 27–28 · AI in Growth & Governance Hospital Ops Workshop · Jul 12 Pre-Summit Seminar · Aug 16 Grand Summit 2.0 · Oct 10–11 Bihar AI Summit · Recap AI Innovation Awards · Aug 22 Grand Summit 2.0 · Oct 2026 Aarambh 2026 Recap
Case Studies Insights & Blog Research Reports Calculators AI in Healthcare Digest
Our Story Leaders @ Ichelon · IN · US · AU Ichelon India · Gurgaon Ichelon Consulting US · Dallas, TX Ichelon Australia · Sydney Speakers & Panelists Client Elevation Programme 🤝 Partner Connect 🇦🇪 ICG UAE Careers
Book a Growth Diagnostic →
We Do It Right. The right diagnosis. The right strategy. The right systems. Giving healthcare leaders the confidence to make better decisions, build stronger operations, and achieve sustainable growth. — Team Ichelon
Trusted by 150+ healthcare & life-sciences brands
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Ophthalmology Marketing · India · 2026 Playbook

Ophthalmology Marketing
Agency in India.

By Rohit Gupta · Business & Growth Lead, Ichelon Consulting Group. Reviewed by Raman Soni, Head of Performance Marketing. Updated July 2026.

Ophthalmology marketing in India differs from generic healthcare marketing on three dimensions: (1) the patient population spans two completely different demographics — young urban professionals researching LASIK (22–38 years, digital-native, price-conscious) and senior patients managing cataract or glaucoma (55–75 years, referred by GP, less digitally active); (2) the LASIK market is India's most price-transparent elective procedure — patients explicitly search "LASIK cost India" and compare across 5–8 providers before booking; (3) compliance complexity is lower than some specialties but AERB licensing must be referenced correctly for laser equipment.

The ICG engagement model
Every practice welcome — retainers starting from ₹20,000/mo (India) or $499/mo (Global).
Goals-Driven engagements · Performance-Linked Payout Models available. Read the full engagement model →
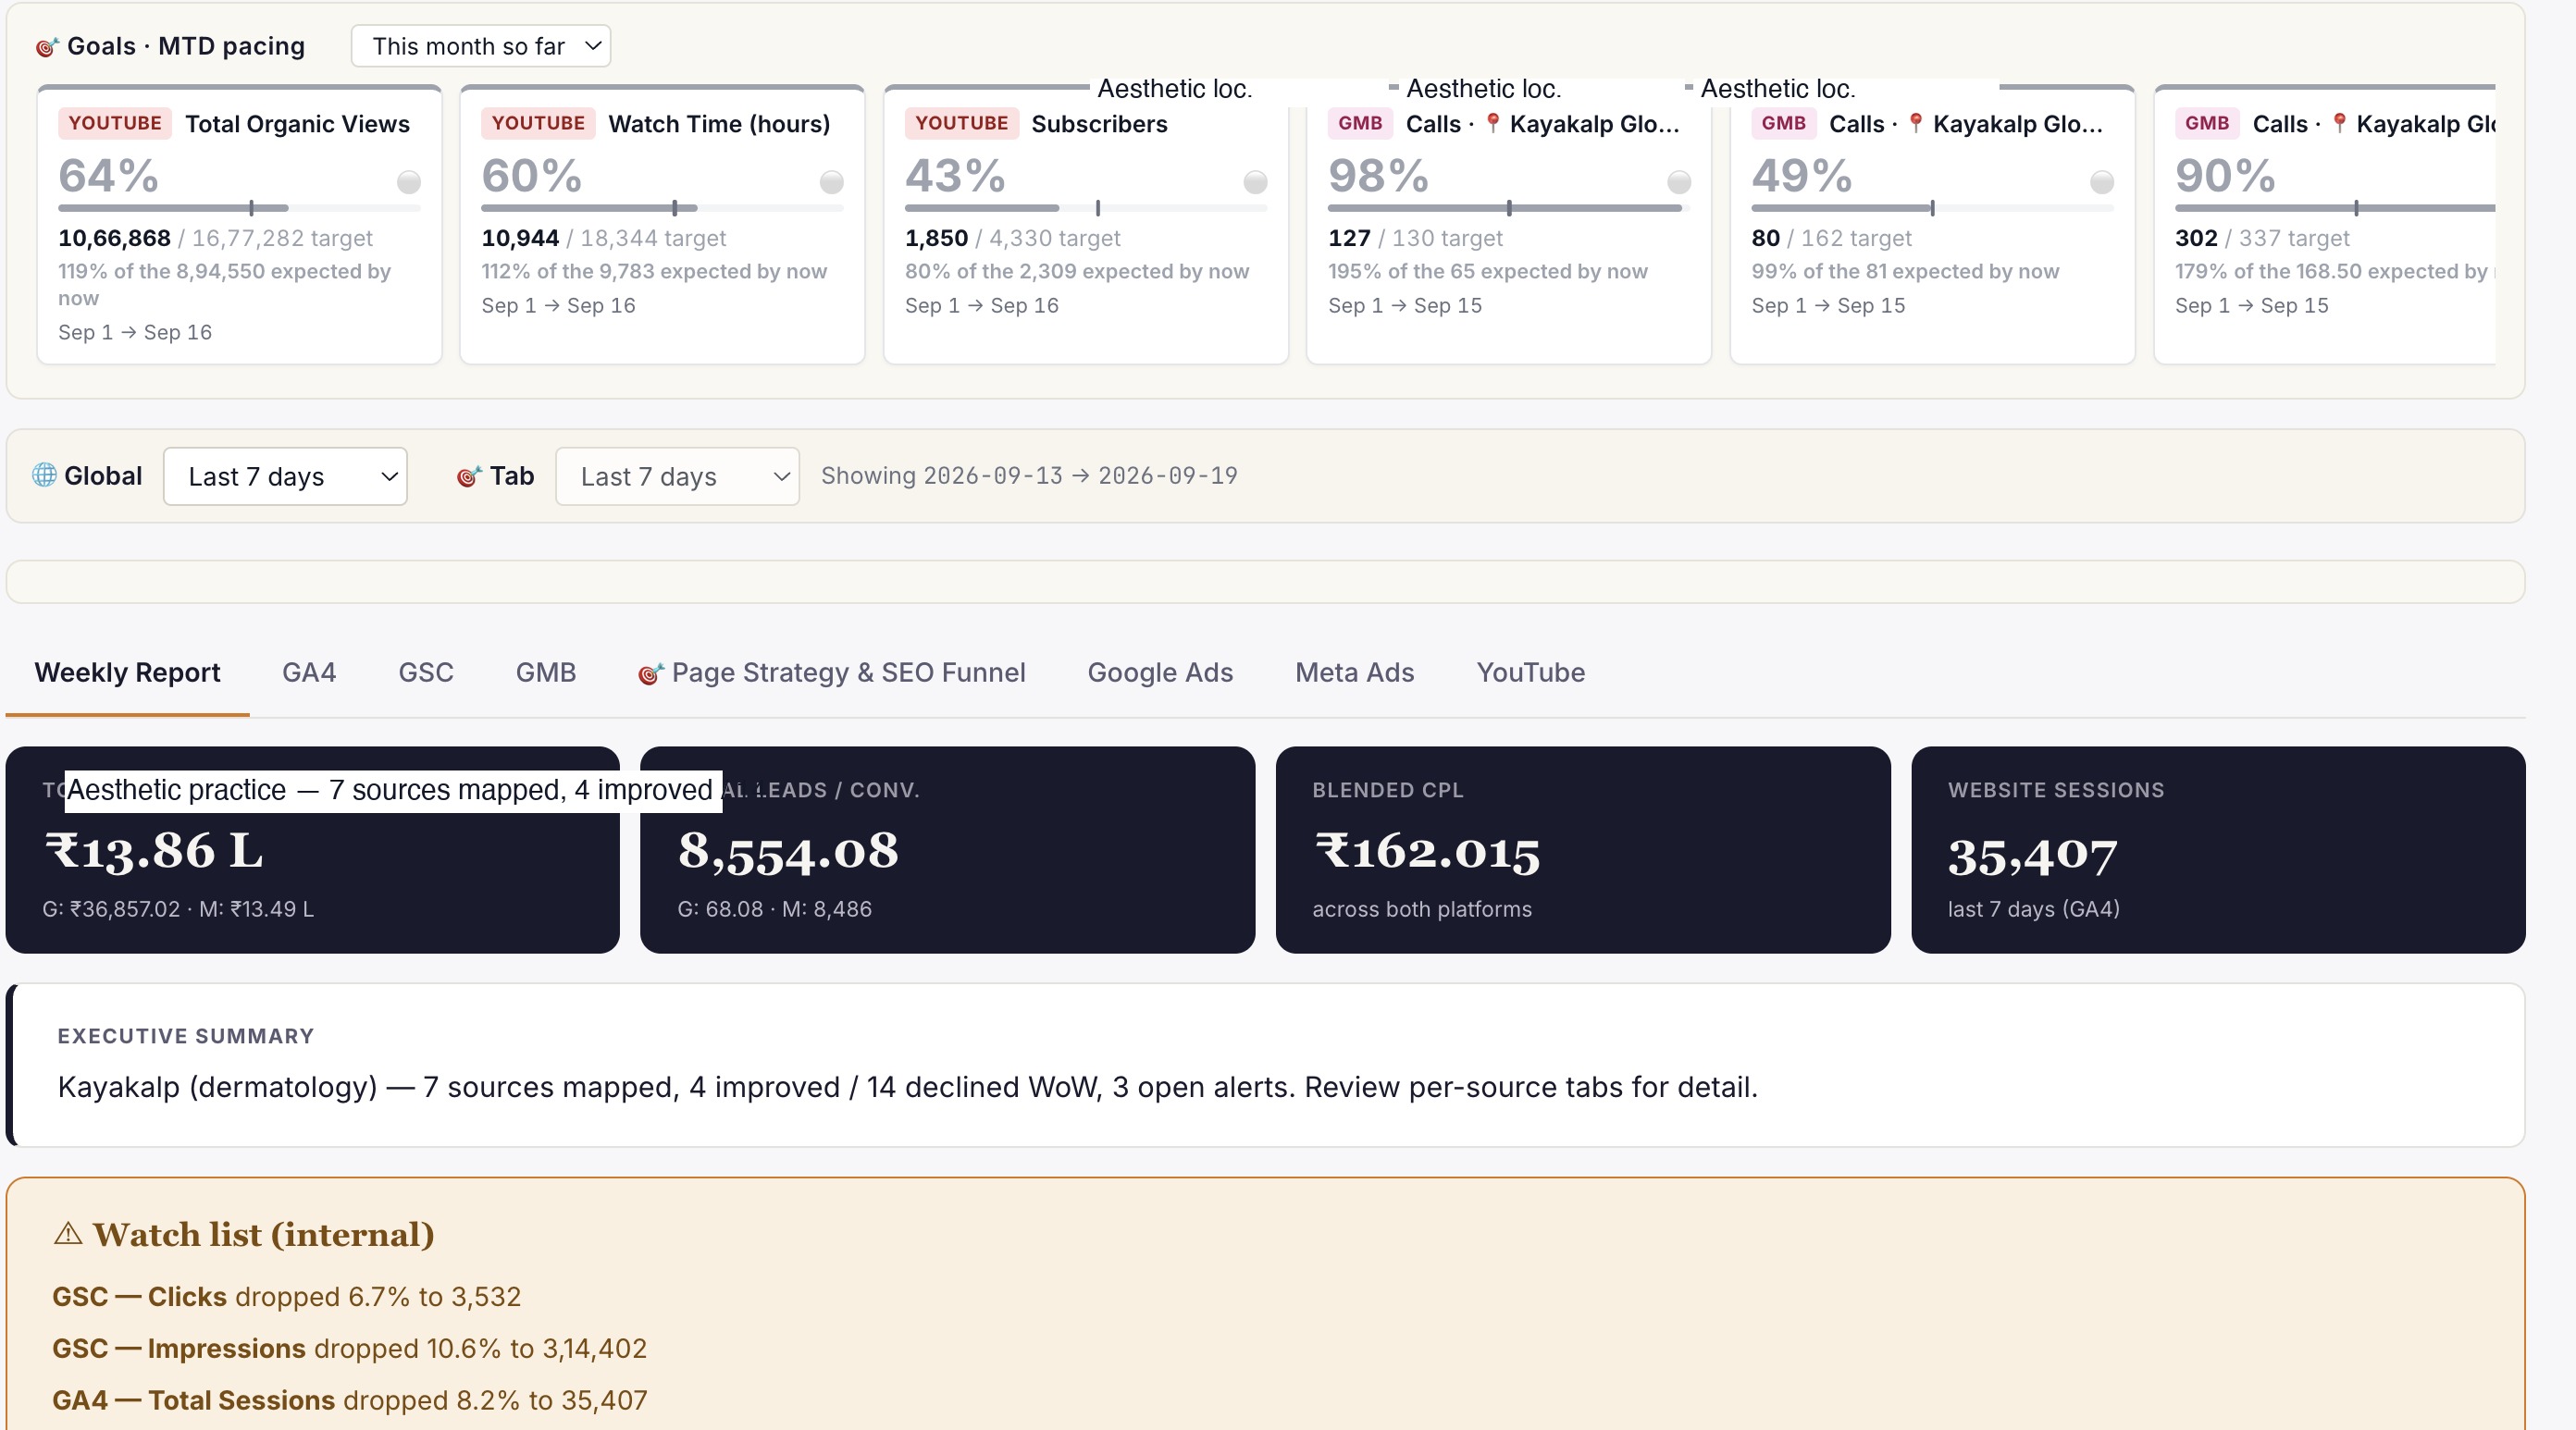
🎯 Ichelon Agency OS See your goals live · client-facing dashboard, updated in real time. Click any screenshot to zoom. Open the full engagement model →
Why ophthalmology marketing is different

Two patients.
Two completely different journeys.

The ophthalmology marketing challenge is managing two audiences with almost nothing in common from a digital behaviour perspective.

The LASIK patient (22–38 years, urban, working professional): Discovers LASIK via Instagram — a friend's post, a sponsored content piece, or a "life without glasses" Reel from a clinic's account. Researches heavily on Google ("LASIK vs SMILE," "LASIK cost India," "LASIK recovery time"). Price-compares actively — 60–70% of LASIK patients get 2–3 quotes before booking. Books online or via WhatsApp. Influenced strongly by review content that specifically mentions post-LASIK vision quality and the experience of the procedure day.

The cataract patient (55–75 years, often from a non-metro or semi-urban background): Referred by a GP or optometrist. Searches (or more likely, their adult child searches) "cataract surgery cost" or "best cataract surgeon near me." More likely to use local directory listings alongside Google. Makes decisions based on proximity, affordability, and insurance/government scheme acceptance. Less influenced by Instagram or YouTube content.

ICG's ophthalmology content architecture explicitly separates these two pathways — LASIK has a dedicated content cluster (procedure comparisons, cost guides, technology explainers) while cataract has a different cluster (what is cataract, IOL types, post-surgery care, CGHS empanelment for cataract).

The LASIK price transparency challenge

LASIK is India's most price-transparent elective medical procedure. "LASIK cost India" generates 100K+ monthly searches. Patients arrive at a consultation knowing the market range (₹15,000–₹85,000 per eye depending on technology). They will ask for and compare quotes.

This price sensitivity changes the marketing approach. ICG's LASIK marketing for client clinics uses a transparency-forward strategy: the website addresses the cost question directly, explains what drives the price difference (blade vs bladeless, LASIK vs SMILE vs LASEK, wavefront vs conventional), and positions the clinic's technology tier and surgeon credentials as the value explanation — not avoidance of the price conversation.

Attempting to hide pricing in LASIK marketing increases bounce rate and reduces consultation booking rate. Addressing it directly with educational context builds trust and improves conversion.

AERB compliance in ophthalmology marketing

Ophthalmic laser systems (excimer lasers for LASIK/LASEK, YAG lasers for capsulotomy) require AERB (Atomic Energy Regulatory Board) licensing in India. While AERB compliance is an operational matter, it is a marketing asset: referencing AERB-licensed laser systems in GBP description and procedure content signals regulatory compliance and equipment legitimacy.

This is particularly relevant for clinics competing in a market where informal laser correction is present in some geographies. "AERB-licensed excimer laser platform" is a factual, verifiable, NMC-compliant trust signal.

The ophthalmology patient decision journey

Three archetypes.
Three separate playbooks.

Archetype 01 · LASIK candidate

30–90 day journey · Instagram to Google to booking

Who they are: 22–38 years. Glasses or contact lens wearer for 5+ years. Stable prescription. Researching permanent vision correction. Usually urban, working professional. Often prompted by a lifestyle trigger (wedding, sports, travel).

Search behaviour: Instagram/YouTube discovery → Google research phase ("LASIK vs SMILE," "LASIK side effects," "Am I a candidate for LASIK?") → cost research ("LASIK cost [city]") → provider comparison ("LASIK clinic near me," "[clinic name] reviews") → booking.

Trust triggers: Technology transparency (blade vs bladeless, specific excimer laser model), surgeon experience (number of LASIK procedures performed), patient reviews mentioning daylight-after-procedure vision clarity, day-1 follow-up protocol, and transparent post-operative care package.

ICG's playbook: LASIK cost explainer page (what affects the price + what we charge + what it includes), LASIK candidate quiz (online screening tool that pre-qualifies and captures contact), Instagram Reels showing the pre-procedure consultation process (NMC-compliant — not the procedure or outcome), Google Ads on LASIK cost + technology queries.

Archetype 02 · Cataract patient or family

2–8 week journey · proximity + insurance-sensitive

Who they are: 55–75 years old, or adult child managing a parent's healthcare decision. Referred by GP or optometrist. Aware of declining vision. Less digitally active than LASIK patient.

Search behaviour: Google ("cataract surgery near me," "cataract operation cost India," "IOL lens types cataract"), local directory listings, word-of-mouth from friends and family. Adult child often does the research.

Trust triggers: Proximity, insurance/CGHS acceptance, patient reviews mentioning painless/quick procedure, clear explanation of IOL options, and the ability to bring family to the consultation.

ICG's playbook: GBP optimisation for local pack visibility (cataract surgery near me), IOL comparison content page (monofocal vs multifocal vs toric), CGHS empanelment displayed in GBP attributes, local directory listings claim and optimisation, post-surgery follow-up protocol described.

Archetype 03 · Paediatric ophthalmology parent

1–4 week journey · child-first search behaviour

Who they are: Parent of a child with squint (strabismus), amblyopia (lazy eye), or refractive error requiring glasses. Usually GP or school vision screening-referred.

Search behaviour: "paediatric ophthalmologist near me," "squint surgery for children," "child eye specialist [city]." Searches from parent's phone, often while caring for the child.

Trust triggers: Paediatric-specific experience ("we see X+ paediatric patients per month"), child-friendly facility description in GBP, reviews from parents mentioning their child's experience.

CPQL benchmarks by ophthalmology sub-vertical

Ophthalmology CPQL — market vs ICG portfolio.
ICG data, rolling 12 months.

Sub-vertical Market avg CPQL ICG portfolio CPQL Treatment LTV Best channel
LASIK / SMILE / LASEK₹1,500–₹4,500₹1,200–₹3,500₹30K–₹85K per procedureGoogle Ads + Instagram
Cataract surgery₹1,000–₹3,000₹800–₹2,200₹25K–₹80K per eyeLocal SEO + local directory listings
Glaucoma management₹800–₹2,000₹600–₹1,500₹15K–₹40K/yearContent + GBP
Paediatric ophthalmology₹600–₹1,800₹500–₹1,200₹8K–₹25K per episodeLocal SEO + healthcare listing platforms
Retina / vitreoretinal₹2,000–₹6,000₹1,500–₹4,000₹40K–₹1.5L per procedureReferral network
Cornea / keratoconus₹1,500–₹4,000₹1,200–₹3,000₹35K–₹1.2LContent + referral
Oculoplasty / cosmetic₹1,800–₹5,000₹1,400–₹3,500₹30K–₹1.5LInstagram + Google

Source: ICG portfolio data, rolling 12 months (Jul 2025–Jun 2026), n=6 ophthalmology engagements. Market averages from industry healthcare marketing benchmarks.

Compliance framework · hospital

Compliance is where most agencies fail.

Hospital advertising sits at the intersection of NMC (per specialist), NABH (institutional), and IRDAI (insurance claims). Multi-specialty hospitals need per-department compliance workflow.

Primary law
NABH standards + NMC Section 6 (per empanelled specialist)

No comparative "better outcomes than" claims without published outcome data. Insurance-empanelment claims must match live TPA lists.

Penalty for violation
Enforcement bite

NABH accreditation suspension + insurance-empanelment revocation

ICG approach
Compliance-first workflow

Every ad + landing page + email routed through a compliance checkpoint before publishing. Zero enforcement actions across 150+ healthcare clients since 2018.

Frameworks ICG operates under

NMC Ethics Code 2026 · DPDP Act 2023 · ART (Regulation) Act 2021 · NABH 6th Edition · Dental Council of India · Schedule J (drug advertising) · UCPMP 2024 · ASCI Healthcare Guidelines

Compliance interpretations current as of October 2026. Enforcement bulletins tracked weekly by ICG's compliance research desk. See our editorial standards for how we source and update these.

How ICG runs ophthalmology marketing

Four tiers.
LASIK, cataract, and paediatric under one roof.

Tier 01 · Local SEO and GBP

Sub-specialty-aware categories + geo-grid

LASIK clinic GBP category: "Lasik eye surgery clinic" + secondary "Ophthalmologist." Cataract-primary clinic: "Ophthalmologist" primary + "Eye care center." Geo-grid scanning reveals LASIK's wider catchment (5–10km in metro) vs cataract's shorter catchment (2–4km proximity-sensitive). Citation building on healthcare listing platforms (high ophthalmology penetration), local directory listings (cataract demographic), Apple Maps, and Bing.

Tier 02 · Paid acquisition

LASIK-specific Google Ads + cost transparency landing

LASIK Google Ads: LASIK cost + technology queries (exact match). Negative: free LASIK, LASIK insurance (LASIK is not covered by most Indian insurance plans — add "insurance cover" as negative to exclude non-converting queries). LASIK landing page: cost transparency section + technology explainer + surgeon credentials + 4-field booking form + WhatsApp CTA.

Tier 03 · Instagram for LASIK

Highest social potential of any ophthalmic sub-vertical

Pre-procedure consultation walkthrough (NMC-compliant — what happens, not "you'll see perfectly"). Day-after-LASIK patient experience content (with consent, experience-focused, not outcome-claiming). Surgeon credential Reels ("10,000 LASIK procedures — here's what I've learned").

Tier 04 · Content authority

LASIK + cataract + paediatric clusters

LASIK cluster: candidate quiz, technology comparison (LASIK vs SMILE vs LASEK), cost guide, recovery guide, FAQ. Cataract cluster: IOL types explainer, what to expect at cataract surgery, recovery and follow-up. Paediatric cluster: squint treatment guide, amblyopia management, when to see a paediatric ophthalmologist.

Sub-vertical deep-dive · Retina

Retina & vitreoretinal —
the emergency-conversion sub-vertical.

Retina behaves differently from every other ophthalmic sub-vertical because the pipeline is dominated by professional referrals and by high-intent emergency search. At a mature retina super-specialty practice, 55 to 75 per cent of new-patient volume arrives via referrals — diabetologists sending diabetic retinopathy screening candidates, general ophthalmologists sending age-related macular degeneration and macular-hole cases, and primary-care physicians sending sudden-vision-loss patients for urgent triage. Digital search closes the remaining 25 to 45 per cent, most of it emergency-intent.

This split shapes the marketing model. The digital budget for a retina practice should look nothing like an aesthetic-derm or LASIK budget. Roughly 15 to 25 per cent of the marketing spend goes to digital acquisition (GBP optimisation for "retina specialist near me", tight always-on Google Ads for emergency-retina search, content authority pages on anti-VEGF, macular hole, and ROP). The remaining 75 to 85 per cent goes to referring-clinician cultivation — quarterly CE lunch-and-learn sessions at partnering diabetology clinics, a formal diabetic-retinopathy referral pathway with shared-report templates, an optometrist referral portal, and case-based content the referring physician can hand a patient.

The high-value differentiator inside emergency retina is response time. A GBP profile that says "vitreoretinal emergencies seen within 4 hours where clinically indicated" and backs it up with a 24-hour-answered phone earns local-pack visibility on "sudden vision loss doctor" and "retinal detachment near me" queries — and, more importantly, converts those searchers at rates two to three times higher than a passive listing. Emergency search-intent case values (vitrectomy plus follow-up: Rs.60,000 to Rs.2.5 lakh) more than justify the on-call cost. See the retina marketing agency deep-dive for the operator's playbook.

Sub-vertical deep-dive · Glaucoma

Glaucoma —
the chronic-care marketing model.

Glaucoma is the only ophthalmic sub-vertical with a two-decade lifetime-value curve. A single 55-year-old newly-diagnosed glaucoma patient managed well contributes Rs.15,000 to Rs.40,000 of clinical revenue per year, retained for 15 to 25 years, and produces the compound word-of-mouth referrals that build a glaucoma reputation. Over the relationship, a single patient represents Rs.3 to Rs.8 lakh of clinical revenue plus the referred family members and friends who screen because of them.

This economic profile makes glaucoma the highest-ROI sub-vertical in ophthalmology for retention investment. Every rupee of marketing spend that produces a glaucoma patient earns back thirty to eighty rupees over the relationship — but only if the retention infrastructure catches the patient at every scheduled visit for the next twenty years. EMR-driven overdue-visit flags, a WhatsApp reminder cadence at 30, 14, and 3 days pre-appointment, an annual-review campaign in November-December for patients who have not booked their yearly OCT and visual-field test, and a medication-refill nudge pathway for chronic-drop patients — none of these look like marketing, all of them are the marketing that matters.

The acquisition side is deceptively simple. Glaucoma is largely symptomless in early stages, which means direct search volume is low — nobody types "glaucoma" until they, a parent, or a sibling has been diagnosed. The acquisition surface is therefore family-history-adjacent Meta targeting, IOP screening camps with the right on-site conversion protocol (a well-run 200-attendee camp produces 3 to 12 new long-term glaucoma patients), and educational content on SLT and MIGS that ranks for the rising surgical-option query volume. See the glaucoma marketing agency deep-dive for the retention SOP and the family-history targeting playbook.

Sub-vertical deep-dive · Cornea & keratoconus

Cornea & keratoconus —
content-led referral capture.

Cornea is a two-audience sub-vertical with a content-heavy top of funnel. The direct-patient side is dominated by 17-to-30-year-old keratoconus searchers — often newly-diagnosed after an optometrist noted suspicious astigmatism on refraction — running 5 to 15 Google and ChatGPT queries before their first specialist consult. The professional-referral side is dominated by general ophthalmologists sending cornea-transplant candidates (DALK, DSAEK, PK) and complex-cornea cases onward.

The content architecture that wins both audiences is a hub-and-spoke pattern. The hub is the definitive keratoconus explainer (what it is, why it progresses, how corneal topography stages it, the treatment ladder from spectacles through specialty contact lenses through C3R through intracorneal ring segments through transplant). The spokes are dedicated pages on C3R (epi-on vs epi-off, accelerated protocols, cost range), corneal topography interpretation, contact-lens types for irregular corneas, and cornea transplant explained by transplant type. Each spoke earns organic ranking on its query family and refers readers back to the hub.

Eye-bank association is an under-used trust signal for the transplant audience. A practice affiliated with a recognised eye bank (LVPEI's Ramayamma International, EBAI-recognised centres) carries verifiable capability signal for both patients and referring clinicians. Display the affiliation on the website, in the surgeon's profile, and in the transplant-service description. See the corneal marketing agency deep-dive for the full content-cluster architecture and the optometrist CE programme structure.

Sub-vertical deep-dive · Oculoplasty

Oculoplasty —
where ophthalmology meets aesthetic marketing.

Oculoplasty is the single ophthalmic sub-vertical whose marketing model borrows more from aesthetic surgery than from mainstream ophthalmology. The primary patient is a 30-to-55-year-old woman researching blepharoplasty (upper or lower eyelid surgery), brow lift, or under-eye correction. The decision cycle is 30 to 90 days, the research is Instagram-heavy, and the trust anchors are the surgeon's before-and-after portfolio, credentials, and consultation experience.

The compliance frame is where oculoplasty gets tricky. NMC and ASCI restrict before-and-after visual outcome claims and superlative positioning ("best eyelid surgeon in Delhi") in a way that mainstream aesthetic marketing has grown around. Compliant oculoplasty Instagram content stays surgeon-led and educational — the surgeon on camera explaining upper-eyelid anatomy, the different techniques (skin-only vs skin-plus-muscle vs SOOF-lift), the consultation experience, the recovery timeline — rather than a visual portfolio of results.

Reconstructive oculoplasty (ptosis correction, entropion, ectropion, orbital tumour management, lacrimal-drainage surgery, thyroid-eye-disease decompression) is a referral-driven segment separate from the aesthetic side. It should be treated as a distinct content cluster with a distinct patient journey — referred by a general ophthalmologist or endocrinologist, less price-sensitive, more clinician-trust-driven. The oculoplasty page on the practice website should present both aesthetic and reconstructive capability clearly, with the reconstructive scope described in the surgeon's clinical profile.

The chain playbook

The multi-location eye hospital
chain playbook.

The Indian eye-hospital chain market has changed. Where five years ago the category was dominated by a handful of legacy multi-city players, the current landscape includes several private-equity-backed Wave-2 chains rolling up regional operators — three to six-branch groups aiming for eight to twelve branches inside 24 months, with meaningful marketing budgets and a demand for a scalable playbook that works branch-by-branch and roll-up-by-roll-up.

Brand versus branch topology: The most consequential architecture decision for a multi-location chain is whether to run one brand-level website with programmatic branch pages, or run separate branch websites that share visual identity but operate independently. The brand-level model wins the head-term SEO (a single domain with 25 to 40 authoritative content pieces outranks six thin branch sites) and is easier to govern. The branch-level model earns better on hyper-local intent ("cataract surgery near {locality}") because it lets each branch build its own GBP-plus-page pairing with locality-specific content. The pragmatic answer for a growing chain is a brand-level primary site with programmatic branch pages that carry locality-specific content, GBP linkage, and localised trust signals.

Central content plus local overlay: Content authority for a chain lives at the brand level — one authoritative cataract-IOL page, one authoritative LASIK cost-transparency page, one authoritative keratoconus hub. Each branch page inherits those assets by reference and overlays locality-specific information: the branch's surgeon list, the branch's empanelments, the local-language content elements (Kannada in Bangalore branches, Bengali in Kolkata branches, Telugu in Hyderabad branches), and locality-specific trust signals (case volumes at this branch, local-language reviews). This model scales — adding a seventh branch means adding one new branch page and inheriting 25 authoritative content assets, not writing 25 new pages from scratch.

Reputation architecture per branch: Each branch needs its own GBP profile, its own review generation SOP, and its own local citation base. Rolling up reviews to a single "corporate" GBP profile is a suspension-risk misstep — Google treats each physical location as a separate entity, and consolidation reads as a policy violation. A well-run chain has a central-review-management dashboard that reads each branch's incoming reviews, alerts on negative reviews within an hour, and routes responses through a centrally-approved but branch-signed reply framework.

Paid acquisition governance: Google Ads should run at the brand-level account with branch-specific campaigns geo-targeted to each catchment. Instagram content should run at a single brand-level handle for content authority plus branch-level story highlights that surface locality-specific information. Central creative production keeps quality consistent; branch-level slot booking and WhatsApp intake keeps conversion friction low.

Roll-up integration: When a chain acquires a regional operator, the marketing integration takes 60 to 90 days done right. Week 1 to 2: audit the acquired brand's digital footprint, GBP profiles, existing content, review base, and paid campaigns. Week 3 to 6: migrate to the chain's brand identity with 301 redirects preserving equity, reclaim GBP profiles under the chain, integrate reviews into the chain's dashboard. Week 7 to 12: publish branch pages, integrate central content authority, launch coordinated Google Ads and Instagram at the new branch. Done right this preserves ranking and captures the acquired book of business; done wrong it can wipe out six to eighteen months of the acquired brand's search equity.

Premium IOL upsell

Premium IOL upsell —
the content architecture that lifts realised revenue per cataract.

The IOL choice is where the majority of realised revenue in a cataract case actually lives. Base surgery bills are standardised across the market; the lens tier is what moves the case value from Rs.25,000 to Rs.80,000 or more. Every one-percentage-point shift in the mix from monofocal to premium (toric, multifocal, trifocal, EDOF) at a mid-volume cataract centre (say 1,200 cases annually) is worth Rs.4 to Rs.8 lakh of annual gross margin. And the shift is largely a content problem, not a sales-training problem.

The Indian cataract patient — and, more importantly, the adult-child researcher who does most of the online research — buys the way a first-time flyer buys their seat: they educate, they consult, they commit. A patient who has read the practice's IOL comparison page before the consultation walks into the consultation ready to have the premium-IOL conversation. A patient who has not read it walks in with monofocal as the default and treats every mention of a premium option as a sales pitch.

The content sequence that consistently lifts premium-IOL uptake by 15 to 25 per cent over a "counsellor pitches premium at the end of the consult" baseline: (1) an IOL comparison page on the website — a genuine educational comparison of monofocal, toric, multifocal, and EDOF lenses, each in one paragraph, with cost ranges rather than fixed numbers, and no language claiming any single lens is universally better; (2) a pre-consultation email or WhatsApp with a link to that page, sent when the appointment is booked; (3) the surgeon or counsellor references the same explainer during the consultation as a shared reference; (4) a post-consultation WhatsApp with the recommended lens, the reason, and the fully-loaded price.

Compliance frame: NMC prohibits outcome guarantees ("with a trifocal you will not need reading glasses") and comparative superiority ("multifocal is better than monofocal"). The compliant framing is capability and trade-off — "trifocal lenses reduce the likelihood of needing spectacles for near vision; the trade-off is a small chance of halos in low light. Your candidacy depends on your specific eye measurements." Honest, structured, and — for the researching child — decisive.

Empanelment as marketing

CGHS / ECHS / PMJAY empanelment
as a marketing asset.

Empanelment display is the highest-leverage single change most Indian eye hospitals can make. A centre that has active CGHS, ECHS, and Ayushman Bharat empanelment but does not display those attributes on the GBP profile, on the homepage, on the cataract landing page, or in the ad copy is leaking qualified demand every single day. The government-scheme patient base for cataract in particular is enormous — CGHS covers 4.4 million beneficiaries, ECHS covers ex-servicemen and their families across India, and PMJAY covers over 500 million — and empanelment is often the deciding factor for these patients.

The right placements: GBP description (a factual sentence — "Empanelled with CGHS, ECHS, Ayushman Bharat"), GBP attributes (Google surfaces scheme acceptance under Payments and Insurance-accepted — enable both), homepage hero band, cataract landing page top-fold trust bar, Google Ads sitelink or callout extension, and website footer. Every one of these placements earns qualified traffic and improves conversion.

State schemes are systematically overlooked. Karnataka's Suvarna Arogya Suraksha Trust, Tamil Nadu's CMCHIS, Telangana and Andhra Pradesh's Aarogyasri, West Bengal's Swasthya Sathi, Maharashtra's MJPJAY, Delhi's DGEHS — each is a marketing lever within its state. A Bangalore cataract centre that displays Suvarna Arogya on GBP will outperform a competitor that does not, all else equal. Display the schemes accurately (never claim an empanelment you do not hold; the fraud risk is real and the ASCI complaint pathway is well-used) and update them promptly when new schemes are approved or existing ones lapse.

YouTube for LASIK

LASIK on YouTube —
long-form authority for the 30-90 day consideration cycle.

YouTube is the most under-used channel in Indian LASIK marketing. Most centres run Instagram Reels and occasionally boost them, and treat YouTube either as a place to upload the same Reels or as a channel too expensive to invest in. Both readings are wrong. The LASIK candidate spends 30 to 90 days in the consideration phase, watches long-form content (10 to 15-minute videos) at higher engagement than 30-second Reels for high-stakes elective medical decisions, and — critically — searches YouTube directly for terms like "LASIK vs SMILE India", "LASIK cost explained", and "day of LASIK surgery experience".

The YouTube content model that works is one high-quality long-form piece per month, produced with the surgeon as the on-camera authority. Topics that consistently earn views, watch-time, and — most importantly — LASIK enquiries: "LASIK vs SMILE vs LASEK: which one is right for you?", "Day of LASIK surgery — what actually happens", "LASIK cost in India explained (2026)", "Am I a candidate for LASIK? The five checks", and "LASIK recovery — what to expect week by week". Each 10 to 15 minutes, surgeon on camera in the clinic, with graphic overlays for the technical bits.

Chapter markers matter. YouTube surfaces long-video content in Google search with rich-result chapter previews on many query types, which meaningfully lifts click-through. Every LASIK long-form should have five to eight chapters with descriptive titles that match sub-queries — "0:00 What LASIK is and how it works", "2:15 The technology options — blade vs bladeless", "5:40 LASIK vs SMILE vs LASEK", "8:20 The cost breakdown", and so on. The description and pinned comment should carry links to the LASIK cost transparency page and the WhatsApp booking flow.

Attribution frame: YouTube-attributed direct conversions are typically single digits per month at moderate volume. The real impact shows up in "how did you hear about us" survey answers ("I watched Dr. X's video on YouTube before booking") and in a 2 to 4-week trailing shift in overall consultation booking rate — the video content has done its trust-building job before the booking channel captures the enquiry.

AI Overview and ChatGPT visibility

AI Overview & ChatGPT visibility
for LASIK and cataract queries.

Google AI Overview and ChatGPT are now the first surface many Indian ophthalmology patients see when they research a procedure. A 26-year-old considering LASIK in 2026 will often ask ChatGPT "am I a candidate for LASIK?" before searching Google, and will scroll past three AI Overview paragraphs on the search result page before reaching the organic listings. The practices that get cited in these AI answers earn a trust anchor that no ad placement can match; the practices that do not get cited effectively disappear from the top of the funnel for that query.

The optimisation work is called Answer Engine Optimisation (AEO), and it borrows from featured-snippet SEO but goes further. Content should be structured for extraction — a plain-language definition sentence at the top of each concept, followed by a bulleted or numbered elaboration, followed by a longer discussion. Headings should mirror the questions candidates type ("What is the difference between LASIK and SMILE?" as an H2 outperforms "LASIK vs SMILE" as an H2 for AEO extraction).

Structured data helps. FAQPage schema with well-written Q&A blocks, MedicalProcedure schema for each procedure page, and Article schema with a named author (a real physician with a biography, credentials, and a photograph) all raise the probability of citation. Author authority is now weighted meaningfully in AI Overview — an article authored by Dr. X, MS Ophthalmology, with a linked biography page carrying credentials and prior publications, ranks and gets cited above the same article without a named author.

The measurement problem is real. AI Overview citations are not directly measurable in GSC yet; ChatGPT citations are not measurable at all. The proxies that work: track the ranking of the specific pages you optimised for AEO on branded queries and long-tail question queries (a page moving from position 8 to position 3 for "what is C3R for keratoconus" is a signal that AEO is landing), track a rising share of "no click" impressions in GSC (a marker that AI Overview is answering the query without the click, which is complicated news — you appeared in the answer but did not get the click), and add "how did you hear about us" fields on the enquiry form with ChatGPT and AI Overview as explicit options.

Optometry referral partnerships

Optometry referral partnerships —
the B2B leg of ophthalmology marketing.

India has more than 40,000 practising optometrists. Most see 15 to 40 patients a day. Every one of them encounters patients with pathology beyond their scope — glaucoma suspicion on IOP or optic-nerve appearance, keratoconus on refraction and retinoscopy, diabetic-retinopathy findings on a routine fundus check, cataract at the referral threshold — and every one of them decides where to refer that patient. The ophthalmology practice that becomes the natural referral destination is the practice that has invested in the optometrist relationship.

The investment structure that works and stays NMC-compliant is educational, not commercial. A quarterly continuing-education programme — 90-minute case-based sessions on rotating topics (glaucoma detection, keratoconus staging, DR screening, cataract referral thresholds), hosted at the practice or online, open to local optometrists, delivered by a specialist consultant — builds durable clinical trust. A referral portal on the website — a simple form that lets an optometrist submit a case (topography scan, OCT, fundus photo, clinical note) for specialist opinion and, where indicated, book a patient into a specific slot with the consult report returned to the optometrist — removes the last friction.

Compliance boundary: NMC does not permit revenue-share, per-referral fees, or commission arrangements between clinicians. A referral-fee model creates ethics-code exposure and is often the deal-breaker that stops a partnership from forming. The compliant model is knowledge partnership plus clinical infrastructure — CE credits, case-based learning, and a fast, professional consult-and-report loop that respects the optometrist's role in the patient's ongoing care.

90-day activation + 12-month calendar

90-day activation timeline
and 12-month editorial calendar.

A well-scoped ophthalmology marketing engagement moves in three 30-day sprints and settles into a rhythm by month four.

Day 0 to Day 30 — Foundation: Audit the current digital footprint — GBP health scores across all branches, existing website content depth, current Google Ads structure, Meta creative catalogue, review counts and rating trends, current CPQL and consult-booking rates. Publish or rebuild the LASIK cost-transparency landing page, the cataract IOL comparison page, and one specialist deep-dive (glaucoma, retina, cornea, or paediatric — whichever sub-vertical is highest priority). Claim and optimise all GBP profiles with correct primary categories, empanelment attributes, and photo sets. Wire WhatsApp intake to a shared inbox with routing rules. Launch the review generation SOP.

Day 30 to Day 60 — Optimisation: First landing-page A/B tests live (headline, price-table position, surgeon photo placement). Google Ads shifts to Target CPA if conversion volume clears the 30-in-30 threshold; if not, refine keyword lists and negatives while staying on manual CPC. Publish the first three long-form content pieces on the priority sub-vertical. Launch Instagram Reels at the target cadence (three per week for LASIK-primary, one per week for cataract-primary and glaucoma-primary). First optometrist CE session scheduled if the practice has a B2B referral leg.

Day 60 to Day 90 — Scale: Google Ads expanded to phrase-match research layer. Second sub-vertical content spine launched. YouTube long-form monthly cadence begins for LASIK-primary practices. Review count showing target trajectory (60-plus new reviews in the quarter for a mid-size centre). CPQL trending toward the target range for the sub-vertical mix.

Month 4 to Month 12 — Editorial calendar: A rolling 12-month content plan built around the specific sub-vertical mix. For an ophthalmology chain with LASIK, cataract, retina, and paediatric services, a working monthly cadence: one deep-dive long-form (rotating across sub-verticals), three Instagram Reels per week (rotating creators and topics), one YouTube long-form (LASIK-heavy), monthly refresh of the empanelment display and scheme mentions as they change, quarterly optometrist CE, and a bi-annual review of the branch-level page and GBP performance across the chain.

CPQL benchmarks · ICG vs market

29–51% below the market
median CPQL, specialty by specialty.

Most ophthalmology marketing agency india pitches sell on CPL. ICG sells on CPQL — Cost Per Qualified Lead — the cost of a lead that actually shows up for a consultation. The difference is often 3–4×. Here is what our 150+ healthcare clients actually pay.

Specialty Market median CPQL ICG median CPQL Difference
IVF & Fertility₹2,400₹1,180−51%
Aesthetic Dermatology₹1,400₹950−32%
Plastic Surgery₹3,500₹2,200−37%
Hair Transplant₹2,100₹1,350−36%
Ophthalmology (LASIK)₹1,800₹1,080−40%
Psychiatry₹2,200₹1,260−43%
Dental (general)₹1,100₹780−29%

Medians from ICG's public CPQL benchmark dataset (Q2 2026), drawn from ICG's live portfolio across Delhi NCR, Mumbai, Bangalore, Hyderabad, Pune, Chennai, and tier-2 cities. Adjust for city: metro CPQLs run 20–35% higher than tier-2 across all specialties.

HealthApex OS · The proprietary stack

Eight platforms. One intelligence layer.

AtomCRM healthcare lead management · Beacon attribution · Hawk CRM intelligence · Phoenix clinic revenue · HealthPro 360 PMS · YODA YouTube intelligence · Agency OS live reporting · AIO Intel AEO+LLM citation tracking. Built in-house since 2018 — included in every ophthalmology marketing agency india engagement.

Explore HealthApex OS → See all eight platforms in detail →
Two products worth knowing

Hawk and YODA.
Standalone offers built for specific gaps.

⏵ Hawk · CRM Intelligence

Is your CRM hiding what it should be showing?

Hawk shows where your leads are leaking: which went cold, which were downgraded by automation, which are recoverable. Free Lead-Leak Audit in 48 hours.

Explore Hawk + free audit →
▶ YODA · YouTube Intelligence

Is your YouTube channel generating patients, or just views?

YODA connects YouTube content to consultation bookings. Patient testimonial videos generate 6.9× more consultations per view than condition explainers.

Explore YODA →
The diagnostic framework

Most healthcare marketing agencies treat symptoms.
ICG diagnoses root causes.

High CPL. Junk leads. Low ROAS. These are symptoms, not problems. ICG's diagnostic framework — built across 150+ healthcare engagements — maps every symptom to its actual root cause and the specific treatment that fixes it.

Symptom Diagnosis ICG Treatment
High CPL across all campaignsPoor channel selectionSLC Matrix
Leads come in, but most are junkInefficient digital operationsDCG Matrix
Leads convert to appointments slowlySales process / telecaller gapsACE Matrix + MIS Tool
CPL keeps rising every monthCross-firing between ad groupsN-Gram + Cross-Firing Analysis
Meta Smart Bidding not optimisingEMQ at 2.5, no first-party signalBeacon CAPI middleware
Traffic is up but enquiries flatWrong T-1 page; no CRODevice ID Tool + OHMRC Model
Invisible to ChatGPT / AI OverviewsNo AEO infrastructureAIO Intel Tool + cluster architecture
Patient database underutilisedNo retention motion on existing patientsPhoenix revenue intelligence
Can't see which leads are leaking from your CRMNo CRM intelligence layer; backward movement invisibleHawk · CRM intelligence + Lead-Leak Audit
YouTube channel has subscribers but no patientsOptimising for views instead of consultation attributionYODA · YouTube intelligence + consultation attribution

Every framework in this table is proprietary to ICG. Calibrated across 150+ live healthcare accounts since 2018. Full ICG methodology → · Glossary →

Complete guides

Read the complete guide
for your category.

Six pillar guides — each 8,000–15,000 words of original ICG methodology, CPQL benchmarks, and live client data. The depth no other Indian healthcare marketing agency publishes.

Healthcare Marketing India — Complete Guide → Doctor Marketing India — Complete Guide → Hospital Marketing India — Complete Guide → IVF Marketing India — Complete Guide → Healthcare Performance Marketing — Complete Guide → Healthcare SEO + AEO India — Complete Guide →

More insights at ichelonconsulting.com/insights · 250+ articles · all healthcare-only

Case study snapshots

Anonymised engagement outcomes
from ICG ophthalmology portfolio.

3-location LASIK centre · Mumbai

Situation: High procedure quality, low digital visibility. CPQL from Google Ads: ₹4,800 (market benchmark). 62 reviews at 3.8★.

Diagnosis: no LASIK cost page (highest-intent query unserved), Instagram inactive, GBP health score 58/100.

Intervention: LASIK cost transparency page published, Instagram content calendar (3 Reels/week), GBP optimised (LASIK category, AERB mention in description, review generation SOP).

Result: CPQL dropped to ₹2,400 at month 4. Review count 62 → 195 at 4.7★. Month-6 LASIK consultations from digital: +88%. (ICG internal data, 2026.)

Eye hospital · Tier-2 city · cataract primary

Situation: 40-bed eye hospital, CGHS empanelled, strong cataract volume from referrals. Zero GBP presence — new patients had to call to find them.

Diagnosis: GBP unclaimed, local directory listings listing with wrong address, zero reviews.

Intervention: GBP claimed + CGHS empanelment noted in description, local directory listings corrected, cataract IOL explainer page added to website, review generation SOP from post-operative follow-up visits.

Result: 8 Google reviews at month 0 → 95 reviews at 4.6★ at month 6. "Cataract surgery near me" top-3 local pack at 4 months. New patient walk-ins from GBP: up 62%. (ICG internal data, 2026.)

6-branch eye hospital chain · North India

Situation: Six-branch chain built via three regional acquisitions and three greenfield openings, running six independent websites and six unmanaged GBP profiles. Combined CPQL Rs.3,900. No shared content authority — each branch's website had 4 to 8 thin pages, no cataract IOL comparison content, no LASIK cost-transparency page, no keratoconus hub.

Diagnosis: Fragmented brand architecture leaking search equity. Two acquired-brand domains still ranking on legacy content but not redirecting to the chain brand. Reviews scattered across six GBP profiles with no central-response cadence — negative reviews sitting unanswered for 30-plus days.

Intervention: Migrated to a brand-level primary site with six programmatic branch pages. 301 redirects preserved acquired-brand equity. Central content authority built at brand level — LASIK cost-transparency page, cataract IOL comparison hub, keratoconus content cluster (hub + 5 spokes), retina emergency-response page. Each branch page carried locality overlay: branch-specific surgeon list, empanelments, local-language elements, and locality reviews. Central-review-management dashboard live with a one-hour negative-review alert. Google Ads consolidated to a brand-level account with six geo-targeted campaigns.

Result: Blended CPQL Rs.3,900 → Rs.1,850 at month 6. Combined organic sessions +240 per cent by month 9 (compounding as the central content authority matured). Consolidated GBP review base 340 → 890 at 4.6-4.7 star average. Two greenfield branch openings hit break-even inside 90 days (versus a chain average of 150 to 180 days pre-consolidation). (ICG internal data, 2026.)

Standalone retina super-specialist · Metro city

Situation: Vitreoretinal super-specialty practice, four consultants, strong clinical reputation but a referral-only pipeline. New-patient volume growth had flattened over 18 months. Digital footprint: a static website with a home page and a contact form, one dormant Facebook page, no GBP optimisation, no content authority.

Diagnosis: Emergency-retina search intent in the metro was completely uncontested — the practice was invisible on "retina specialist near me" and "sudden vision loss doctor" queries despite being the referral destination the local ophthalmology community actually used. No B2B infrastructure to formalise the diabetologist relationships that were producing ad hoc referrals.

Intervention: Full retina content spine built at brand level — anti-VEGF explainer, macular hole surgery page, ROP awareness content for paediatricians, diabetic-retinopathy screening hub. GBP claimed and optimised with a "vitreoretinal emergencies seen within 4 hours" description. Emergency-intent Google Ads (retina emergency, sudden vision loss doctor) tightly geo-targeted with call-only creative and 24-hour scheduling. Diabetologist partnership programme structured: three anchor partnerships formalised in the first quarter with shared-report templates and quarterly CE lunch-and-learns. Optometrist referral portal published on the website.

Result: Direct organic-and-paid new-patient volume 0 → 42 in month 6 (previously 0 — the practice was 100 per cent referral). Formalised diabetologist referrals +180 per cent in the first year. Emergency-retina case volume from Google-search origin: 6 to 14 per month by month 6, at CPQL Rs.4,400 blended (against case values easily justifying the spend). (ICG internal data, 2026.)

Corneal referral centre · Tier-1 city

Situation: Corneal referral centre with keratoconus, contact-lens management, and cornea transplant capability. Two corneal consultants, one on-site optometry team. Website was a general-ophthalmology site with a single "cornea services" page. healthcare listing platforms profile claimed but bare. No content authority on the query cluster that matters — keratoconus, C3R, corneal topography, cornea transplant.

Diagnosis: The keratoconus search cluster in the city was under-served, and the practice's clinical strength was not reflected online. General ophthalmologists in the local network were referring cornea patients to two other centres because those centres had visible corneal content authority and the practice did not.

Intervention: Built the full keratoconus content hub-and-spoke: definitive keratoconus explainer (hub), C3R/CXL page, corneal topography interpretation page, contact lenses for irregular corneas page, intracorneal ring segments page, cornea transplant (DALK/DSAEK/PK) page. Each page authored by a named corneal consultant with byline, credentials, and photograph. Eye-bank affiliation displayed on the site and in the surgeon's profile. Quarterly optometrist CE programme launched with 45 to 60 attending optometrists per session. Referral portal wired to a shared inbox with 48-hour specialist-response commitment.

Result: Direct keratoconus consultations +310 per cent in year one (from a low base of 12 per month to a rolling 49 per month). Cornea transplant referrals from partner ophthalmologists +140 per cent. Optometrist referral share of new patients grew from 8 to 27 per cent of monthly new-patient volume. The centre is now the top ranked "keratoconus specialist" and "cornea specialist near me" result for the city. (ICG internal data, 2026.)

YouTube Marketing · ICG YODA Intelligence

Hospital marketing on YouTube: 12-25 specialty funnels run in parallel.

Multi-specialty hospitals serve 12-25 specialty audiences simultaneously. Each has its own CPQL economics, language preference, and content format. ICG's YODA tool segments per-specialty performance + reallocates content investment monthly based on actual consult attribution.

Aggregated lifetime views
180M+
Specialties analysed
9
Consult attribution
Per-video
Read the State of Doctor YouTube India 2026 (flagship) → Explore ICG's YouTube Marketing service →
Frequently asked

About ophthalmology marketing
agencies in India.

ICG LASIK CPQL target: ₹1,200–₹3,500 per qualified enquiry. Market average is ₹1,500–₹4,500. The primary driver of CPQL efficiency is LASIK cost transparency on the landing page — clinics that answer the price question directly convert significantly better than those that drive users to call for pricing.

Yes — individual clinic LASIK outcome claims ("98% of our patients achieve 6/6 vision") are NMC-prohibited outcome promises. You can cite published population-level data from peer-reviewed journals with attribution. Your pre-operative consultation is the NMC-compliant conversion point: "your assessment will determine your candidacy and expected outcome."

Both are essential in different ways. Instagram builds awareness and trust over weeks (LASIK consideration cycle). Google Ads captures existing intent (patients ready to compare and book). A clinic that runs Google Ads without Instagram misses the trust-building stage. A clinic that only does Instagram misses the bottom-of-funnel capture. ICG runs both simultaneously for LASIK clients.

Primary: "Lasik eye surgery clinic." Secondary: "Ophthalmologist," "Eye care center," "Optometrist" (if optometry services are offered). Do not add categories that don't match actual services — this is a suspension risk.

Completely different strategy. Cataract: local SEO-dominant (proximity-sensitive patient), local directory listings optimisation (older demographic), insurance/CGHS empanelment as decision factor, educational content on IOL types. LASIK: Instagram and Google Ads-dominant, price transparency as conversion lever, younger digital-native patient, technology differentiation (SMILE vs LASIK vs LASEK) as trust builder.

Metro city LASIK centre: 100+ reviews at 4.4★ minimum. Tier-2 cataract hospital: 50–80 reviews at 4.3★ minimum. Review velocity targets: LASIK (high post-procedure positive sentiment) — 15–25 new reviews per month achievable. Cataract (older patients, lower review-writing propensity) — 8–15/month realistic.

The compliant framing is capability and trade-off, never outcome guarantee. 'Trifocal lenses reduce the likelihood of needing spectacles for near vision; the trade-off is a small chance of halos in low light. Your candidacy depends on your specific eye measurements' is compliant. 'With a trifocal you will not need reading glasses' is not. The content should educate the researcher (usually the adult child), let the surgeon or counsellor personalise during the consult, and reserve pricing conversation for after the clinical assessment.

Instagram is a trust-signalling channel for cataract, not a lead-generation channel. The 55-to-75-year-old cataract patient is not on the platform; the adult-child researcher is. An active feed — one Reel per week, surgeon-led or a consented post-op patient story — signals to the researcher child that the practice is modern and current. Direct patient acquisition for cataract comes from GBP local pack, empanelment display, and content — Instagram supports trust but does not drive volume.

A DR screening programme is a B2B marketing problem, not a consumer marketing problem. The stack: (1) formal referral pathways with local diabetologists and endocrinologists with shared-report templates and a 48-hour report-back SLA; (2) a quarterly CE lunch-and-learn on DR staging and management, hosted at partnering diabetology clinics; (3) a dedicated DR screening landing page ('screening for patients of {referring practice}') with WhatsApp booking; (4) a diabetologist-facing PDF summary of the practice's DR staging and treatment pathway. NMC prohibits per-referral fees; keep the partnership educational and clinical. A single active diabetologist referring 3 to 5 patients monthly becomes a Rs.6 to Rs.15 lakh annual pipeline.

The pragmatic architecture is a brand-level primary site with programmatic branch pages. Central content authority (LASIK cost transparency, cataract IOL hub, keratoconus cluster) at the brand level. Each branch page overlays locality-specific content — surgeon list, empanelments, local-language elements, locality reviews. GBP profiles remain per-branch (Google treats each physical location as a separate entity; consolidation is a policy risk). Google Ads at brand-level account with per-branch geo-targeted campaigns. Instagram at a single brand handle for content authority plus per-branch story highlights. This scales — a seventh branch means one new branch page, not 25 new content pieces.

The ICG technology stack

Nine tools. One compounding system. HealthApex OS
Built in-house. Deployed in every engagement.

ICG's results are reproducible because they are built on proprietary infrastructure — not agency intuition or generic tools. These nine HealthApex OS platforms are what power every ICG engagement.

Healthcare CRM

AtomCRM

Healthcare CRM & Lead Management

ICG's healthcare-specific CRM and lead management system. Specialty-configured funnel stages for IVF, dental, aesthetic, ortho, hospital OPD. 1-click CAPI + GCLID via Beacon. Hawk intelligence built in. DPDP-compliant by architecture. Includes the AtomCRM calling app, which replaces a traditional IVR. Live at 80+ healthcare centres in India.

  • Specialty-specific funnel stages, not generic SaaS pipeline
  • 1-click CAPI + GCLID via Beacon attribution
  • Telecaller leaderboard + adherence scoring native
  • DPDP Act 2023 compliant by architecture
Explore AtomCRM →
Business Layer

Hawk

CRM Intelligence & Lead-Ops MIS

Sits as the business intelligence layer above your CRM — AtomCRM or any other CRM you run, including custom builds. Shows where leads are leaking, which effort is wasted, and which good leads were quietly downgraded by automation — not by a human decision.

  • Sits above your existing LMS — no replacement
  • 83% of effort goes to dead leads — surfaced Day 1
  • ~75% qualified-lead downgrades by automation
  • Free Lead-Leak Audit in 48 hours
Explore Hawk + free audit →
Attribution Core

Beacon

Attribution Engine & CAPI Middleware

Sits at the centre of every ICG attribution architecture. CAPI middleware connecting Meta Ads, Google Ads, WhatsApp and IVR to your CRM. Lifts Event Match Quality from 2.5 to 6+, reducing CPM 30–40% from the same budget.

  • Server-side CAPI — bypasses iOS privacy changes
  • EMQ 2.5 → 6+ across portfolio
  • 30–40% CPM reduction from EMQ lift alone
  • Multi-touch: ad → consultation → revenue
Explore Beacon →
Practice Management

HealthPro 360

PMS with built-in revenue intelligence layer

A PMS built to track cross-sell and up-sell opportunities within your existing patient base. 12 modules covering OPD, IPD, Pharmacy, Labs, Billing, Inventory, Patient Portal, Smart Scheduling, RBAC, AES-256 encrypted storage.

  • Only PMS with built-in Revenue Intelligence
  • Cross-sell signal tracking within existing patients
  • 12 modules: OPD, IPD, Pharmacy, Labs, Billing+
  • Audit trails + RBAC + AES-256 encryption
Explore HealthPro 360 →
Revenue Layer

Phoenix

Revenue intelligence built over your existing PMS

If you already have a PMS, whichever one it is, Phoenix builds the business intelligence layer on top of it without replacement. Built for single clinics and multi-centre chains alike.

  • Works over your existing PMS — no migration
  • Daily action queue: Prevent Loss / Maintain / Grow
  • Catches unbilled services, collection gaps, lapsing patients
  • CPQL variance ₹620–₹3,800 → ₹680–₹1,420
Explore Phoenix →
YouTube Intelligence

YODA

YouTube analytics that measures patients, not views

A YouTube intelligence platform built for healthcare business outcomes. Connects video performance to actual consultation bookings — not views, not subscribers. Patient testimonial videos generate 6.9× more consultations per view than condition explainers.

  • Consultation attribution per video — not views
  • Demand-gap: what patients search that your channel misses
  • 50+ doctor channels tracked across India
  • AIO readiness scoring: which videos AI tools cite
Explore YODA →
Governance & Transparency

Agency OS

Full transparency. Instant diagnosis. Zero surprises.

ICG's centralised governance platform — every client sees everything in real time, and ICG's team sees every problem the moment it surfaces. 30+ real-time alert systems fire the moment a metric drifts outside its performance envelope.

  • GSC, GA4, Google Ads, Meta Ads, IVR — one live view
  • 30+ real-time alert systems per account
  • CPQL drift alert at >15% week-on-week change
  • Client login: full transparency on your account
Explore Agency OS →
AEO & LLM Intelligence

AIO Intel

AI Overview + LLM citation tracking, healthcare-tuned

Knows the moment ChatGPT, Perplexity, Google AI Overviews and Gemini cite your brand in patient answers — and which content drove the citation. Bot-aware dashboard with GA4-registered custom dims (AIO source, AIO referrer) and IndexNow + GSC API integration.

  • Live tracking across ChatGPT / Perplexity / Google AIO / Gemini
  • Bot-aware: knows human vs scraper traffic
  • Custom GA4 dims register AIO source + referrer
  • IndexNow + GSC API: content surfaced to LLMs within hours
View AIO Intel dashboard →
Competitor Intelligence

Prism Spy

Every Meta + Google ad your competitors run, watched daily

Tracks 75+ Indian healthcare brands, 2,150+ active ads, ₹50Cr+ aggregate ad spend visibility per month. Surfaces what's working, what's been killed, what offers are emerging. Powers every ICG Meta Ads brief, Performance Marketing diagnostic, and IVF / derm / dental specialty campaign with real competitive intelligence.

  • 75+ brands tracked across 30+ healthcare specialties
  • 2,150+ active ads · daily refresh
  • Activity Feed: every spend / hook / pause logged
  • Offers Intelligence: 250+ offers in market tracked
Explore Prism Spy →
GBP Intelligence Platform

Angryturtle

Every Google Business Profile scored, tracked, protected, and grown from one command centre

ICG's proprietary Google Business Profile intelligence platform. Scores every listing across 7 dimensions, tracks rank on a live geo-grid across your actual service area, audits NAP + citations, monitors 531 suspension-risk factors continuously, and drafts Google Posts on cadence. Currently managing 143 healthcare listings with 0 suspensions and 4.76★ portfolio average across 28,137 reviews.

  • 143 listings under management · 0 suspensions · 4.76★
  • 7-dimension Health Score + 5-factor Rank OS per listing
  • Geo-grid rank tracking + NAP + Citation audit + Profile Shield
  • NMC + NABH + ART Act + DPDP compliance built into every content + review workflow
Explore Angryturtle →

Every ICG engagement runs on some combination of these ten HealthApex OS tools. The diagnostic determines which combination is right for your practice.

Explore HealthApex OS → See the full stack live on your account — free 30-min audit →
The team behind your account

Every diagnostic is led by Sr. Leadership.
You'll know their names before the engagement begins.

ICG was built by three IIT BHU engineers who entered healthcare marketing with a specific intent: to build the tools that didn't exist and run the campaigns that most agencies couldn't. When you book a diagnostic, a member of our Sr. Leadership team leads it. Not an account manager. The people accountable for what you're evaluating.

The ICG team — 60+ healthcare marketing specialists at Gurgaon HQ

60+ specialists.
One growth engine.

Performance marketers, analysts, AI engineers, content strategists, and operations specialists — all healthcare-only. Headquartered in Gurgaon since 2018.

Rohit Gupta — Leader, ICG

Rohit Gupta

Business & Growth Lead & Director

IIT BHU · IIM Rohtak

Rohit's first question in every diagnostic: "When you ask your agency why patients aren't booking — what do they say?" He says the answer tells him more than any dashboard.

Full profile →
Abhash Kumar — Leader, ICG

Abhash Kumar

Strategy & Analytics Lead & Director

IIT BHU · IIM Bangalore

Abhash built Beacon because most agencies couldn't answer one question: "Which of my campaigns generated that consultation?" He decided the problem was solvable in code. It was.

Full profile →
Deep Das — Leader, ICG

Deep Das

Technology & AI Lead & Director

IIT BHU

Deep built the 4-Bot patient lifecycle system after watching a client lose 60+ qualified leads in one week to a 6-hour WhatsApp response window. He decided the problem was solvable in code. It was.

Full profile →
HealthApex OS Pricing · All-Inclusive · Billed Annually
₹2,999 – 3,999/month
Single Tool
Hawk CRM intelligence overlay (₹2,999), HealthPro 360 / Phoenix alone (₹3,999 each). AtomCRM ₹50K/- setup + ₹799/- per telecaller/mo.
₹4,999 – 11,999/month
Bundled Suite
AtomCRM ₹50K/- setup + ₹799/- per telecaller/mo. HealthPro 360 + Patient Portal ₹7,999. Operations Suite (HealthPro + Phoenix + Portal) ₹11,999.
₹14,999/month
Complete HealthApex OS ★
All 8 tools: AtomCRM + Hawk + Beacon + Phoenix + HealthPro 360 + YODA + Agency OS + AIO Intel. Best value. Full integration.

Transparent. Billed annually. No hidden integration fees. Most Indian clinics save 60-80% vs an enterprise CRM suite or a 5-vendor multi-tool stack. Complete HealthApex OS at ₹14,999/month is 40-60% cheaper than maintaining a multi-vendor stack — plus you get unified data, one compliance officer, one founder-led engagement. Enterprise tier (hospital networks, multi-brand, custom modules): ₹50,000 – ₹3,00,000/month, founder-led.

Book the free 30-min diagnostic →
Selected ICG clients

Healthcare brands ICG
has worked with.

A representative slice of the 150+ healthcare brands ICG has delivered for across India. Full client list available under NDA during a Brand and Growth Diagnostic.

Read full client case studies →

Eye hospital client video stories

Hear it from the eye hospitals and LASIK centres ICG works with.

Dr. Ruchika Gupta
Founder, Tulasi Healthcare · Tulasi Healthcare (Mental Hospital) · Gurgaon

"Mental health marketing requires a different sensitivity. ICG built compliance-aware campaigns that respect both patients and our..."

Dr. Vikas
Bariatric Surgeon · Medanta · Gurgaon

"Bariatric surgery patients need a long consideration cycle. ICG built a content + paid system that respects that timeline."

Dr. Ramanjit Singh
Dermatologist · Medanta Hospital · Gurgaon

"Working with ICG felt like working with an in-house growth team that happens to specialise in healthcare."

See all client video testimonials →
Sources & methodology
View sources cited on this page
  • All India Ophthalmological Society (AIOS) clinical guidelines
  • NMC Ethics Code 2026 — nmc.org.in
  • AERB — LASIK laser equipment licensing guidelines
  • Industry healthcare marketing benchmarks
  • ICG portfolio data (n=6 ophthalmology engagements, Jul 2025–Jun 2026)
Named clients on this engagement

3 clinical leaders who trust ICG.

Every named client below has a public testimonial on /testimonials — named with consent, quoted verbatim. No composite testimonials, no invented names.

AK
Dr. Arvind Kumar
Medanta · Delhi
See all client testimonials →
VS
Dr. Vikas Singhal
Medanta · Gurgaon
See all client testimonials →
AS
Dr. Arvinder Soin
Medanta · Gurgaon
See all client testimonials →

Named-client consent verified October 2026. Every client listed has approved their testimonial publication under ICG's editorial standards. If you're an ICG client and want your named testimonial removed from these listings, WhatsApp +91 81302 26224 and we'll de-list within 24 hours.

Ready to build an
ophthalmology marketing engine?

Start with a complimentary 30-minute Ophthalmology Growth Diagnostic from ICG. For LASIK centres, multi-location eye hospitals, and cataract-primary practices across India.

Chat with Sr. Leadership
🎯 Goals-Driven engagements · Performance-Linked Payout Models
Chat with Sr. Leadership