Healthcare Pharma & Life Sciences Other Industries
All Services Performance Marketing ChatGPT Ads India · NEW Social Media Marketing SEO & AEO / LLM YouTube Marketing LLM Optimization Brand & Growth Consulting AI Solutions Industries We Serve
Enterprise Hub · All Solutions + Services Growth Transformation AI Transformation Revenue Operations Fractional CGO Growth Operating System Executive Growth Advisory
Clinic Launch Programme (Hub) NABH Consulting India Healthcare Brand Launch Clinic SOP Creation Logo Design (Healthcare) Brand Book Creation Clinic Launch Marketing D2C Brand Launch Clinic Interior Design
Workforce Hub For Employers — post a requirement For Professionals — register Public Openings Training Academy AI Training Flagship
Hawk · CRM Intelligence (NEW) YODA · YouTube Intelligence Angryturtle · GBP Intelligence (NEW) Prism Pulse · Instagram Analytics (NEW) Beacon · Attribution Agency OS · Dashboards Phoenix · Clinic Revenue HealthPro 360 · PMS/HMS AI Patient Lifecycle Bots AI Lead Management System Smart Appointment System Healthcare CRM Patient Feedback System AI, Analytics & Automation Digital Transformation Calculators Free Digital Health Audit →
All 13 calculators → 🎯 Business Exploration Matrix (New) Dental Clinic Setup IVF Clinic + Lab Setup Multi-Specialty Hospital Setup Aesthetic / Cosmetology Clinic Dermatology Clinic Setup Generic Clinic Setup Physiotherapy Clinic Setup Diagnostic Centre Setup CAC Calculator CPQL Calculator Franchise ROI Calculator Revenue Leakage Calculator CRM ROI Calculator
All Events Workshop 1 · Jun 13 · AI in Clinical Practice Workshop 2 · Jun 27–28 · AI in Growth & Governance Hospital Ops Workshop · Jul 12 Pre-Summit Seminar · Aug 16 Grand Summit 2.0 · Oct 10–11 Bihar AI Summit · Recap AI Innovation Awards · Aug 22 Grand Summit 2.0 · Oct 2026 Aarambh 2026 Recap
Case Studies Insights & Blog Research Reports Calculators AI in Healthcare Digest
Our Story Leaders @ Ichelon · IN · US · AU Ichelon India · Gurgaon Ichelon Global · Dallas, TX Ichelon Australia · Sydney Speakers & Panelists Client Elevation Programme 🤝 Partner Connect 🇦🇪 ICG UAE Careers
Book a Growth Diagnostic
We Do It Right. The right diagnosis. The right strategy. The right systems. Giving healthcare leaders the confidence to make better decisions, build stronger operations, and achieve sustainable growth. — Team Ichelon
Trusted by 150+ healthcare & life-sciences brands
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
i Quick answer · 2026

A dermatology marketing agency in India splits medical + aesthetic funnels (medical on Google Search, aesthetic on Meta Reels). Real CPL ₹250-₹700. Package-based aesthetic pricing (6-month plans) with 3-5× LTV vs single-visit. NMC + DMRA compliant. Retainers ₹35K-₹4L/mo.

Live accounts
30+
Derm + aesthetic clinics
CPL benchmark
₹250-₹700
Meta + Google
Aesthetic LTV lift
3-5×
Package vs single-visit
Dermatology Marketing · India · 2026 Playbook

Dermatology Marketing
Agency in India.

By Rohit Gupta · Business & Growth Lead, Ichelon Consulting Group. Reviewed by Hanuman Sihag, SEO Reviewer. Updated September 2026.

Medical dermatology in India is not a single market. It is eight distinct condition verticals sitting under one clinical roof — acne, psoriasis, vitiligo, eczema, alopecia, fungal, pigmentation and rosacea — each with its own buyer, its own decision cycle, its own price band and its own compliance minefield. The dermatologist-founder practice that treats it as one funnel spends three times what it should on acquisition. The chain that industrialises the eight-vertical split compounds referrals for a decade. This page is the operator manual for both.

The ICG engagement model
Every practice welcome — packages from ₹20,000/mo.
Goal-linked packages · Fixed retainer + Goal-based Variable Pay · 19-month average client retention — industry-leading. Read the full engagement model →
{-- Agency OS thumbnail · 2026-09-20 --}
Backed by App\Support\NamedExperts::get(). --}}
Medical vs aesthetic dermatology

Two categories.
Two completely different marketing models.

Medical dermatology and aesthetic dermatology sit under the same MD degree and often inside the same clinic, but the marketing model that wins one loses the other. Medical dermatology is a chronic-care, referral-heavy, insurance-adjacent, retention-defined business. Aesthetic dermatology is an elective, discretionary-spend, Instagram-heavy, price-transparency business. The buyer, the search behaviour, the trust anchors, the compliance surface and the LTV curve are all different. Clinics that run one funnel for both dilute their positioning and see cost-per-qualified-lead drift 40 to 80 per cent above the achievable band.

The medical dermatology patient arrives with a condition that is not going away — acne persisting past over-the-counter care, a psoriasis plaque that flared last winter, a vitiligo patch a family member noticed, hair thinning that a barber flagged, eczema on a child that the paediatrician escalated. The decision surface is trust, expertise and clinical infrastructure. Price matters, but not the way it does in aesthetics.

The aesthetic dermatology patient arrives with a discretionary spend — a HydraFacial before a wedding, a chemical peel after Diwali, laser hair reduction as a lifestyle project. The decision surface is price transparency, before-and-after inspiration, brand aesthetic, and social proof. Insurance is irrelevant. Chronic-care retention is irrelevant. The category behaves closer to a premium beauty service than to medicine.

ICG's aesthetic-side playbook lives at the aesthetic dermatology industry hub. This page is the medical-side operator manual. Nothing that follows is aesthetic strategy retooled — every choice below is derived from the specific unit economics of eight medical dermatology sub-verticals.

The three regulators

NMC Section 6, ASCI, and Meta Personal Attributes —
why forty per cent of first-time skin creative gets blocked.

Every dermatology creative asset a clinic ships passes through three compliance filters before it reaches a patient. Miss any one and the asset either does not run, gets an ad-account strike, or triggers an NMC ethics complaint. The dermatology category collides with all three more frequently than any other medical specialty in India.

NMC Section 6 of the Professional Conduct Regulations 2002 governs what a registered medical practitioner can say in advertising. The relevant clauses for dermatology: no direct outcome claim ("clears acne in 30 days" is prohibited), no comparative superiority naming the doctor ("best dermatologist in Delhi" is prohibited), no testimonial that names or shows a specific patient in a way that promotes the doctor, and no before-and-after imagery used as an advertising claim. The Section is enforced through State Medical Councils, and complaints from competitors are the primary trigger.

ASCI (Advertising Standards Council of India) layers on top with the CAP Code and its healthcare guidelines. ASCI is faster to move than the NMC route — a competitor complaint typically produces a ruling in six to ten weeks — and ASCI rulings force ad withdrawal across platforms. The dermatology traps: superlatives without substantiation ("India's most trusted skin clinic"), guaranteed-result language ("100 per cent pigmentation removal"), and price claims without the actual price condition disclosed ("starting Rs.499" without noting the consultation-only scope).

Meta Personal Attributes policy is the operational chokepoint most clinics do not see coming. Meta's ad review machine rejects any creative it reads as implying the viewer has a specific personal attribute — a skin condition, a hair loss pattern, an age, a body weight. "Struggling with acne? Book a consult" is a rejection. "Learn about acne treatment options" is not. In our portfolio, roughly forty per cent of first-time dermatology creative — even from clinics that have run Meta ads for years in adjacent categories — is blocked on this policy. This is where a specialist agency stops being optional. Clearing Meta review at scale requires a creative rulebook that is written into every brief, every hook, every caption and every landing page copy line before the asset gets uploaded.

The three-regulator craft is not additive — it is intersectional. A line that passes NMC can fail ASCI. A line that passes both can be blocked by Meta. The compliant dermatology creative library is smaller than the intuitive one, and building it is the work.

The eight condition verticals

How the medical dermatology category actually splits.
Eight verticals. Eight buyers. Eight funnels.

Vertical 01 · Acne

Volume engine · 14-28 buyer · Reels-primary

Acne is the category's volume engine. The buyer is 14 to 28, mobile-native, Reels-primary, price-comparing. The parent-buyer for teen acne (age 12 to 17) is a second, quieter funnel that most clinics under-serve. CPQL runs Rs.180 to Rs.450 in ICG portfolio benchmarks for medical acne clinics. Isotretinoin content, price-transparency landing pages and the mall-clinic chain model are covered in depth on the acne marketing agency page.

Vertical 02 · Psoriasis

Chronic-care model · GP-referral · 5-10 year LTV

Psoriasis is not a lead-gen category — it is a chronic-care category. The economics live in retention, not acquisition. GP-referral engines, biologics content (secukinumab, adalimumab biosimilars, risankizumab) and NB-UVB phototherapy positioning drive the model. LTV runs Rs.60,000 to Rs.1.8 lakh across the relationship. Full playbook on the psoriasis marketing agency page.

Vertical 03 · Vitiligo

Long-decision cycle · community trust · YouTube-heavy

Vitiligo carries India's longest dermatology decision cycle — 90 to 180 days average from first search to first consult. The buyer is stigma-sensitive, community-driven, and researches on long-form YouTube more than on Reels. Autologous grafting versus topical versus phototherapy is the education stack. Regional-language content matters more here than in any other sub-vertical. See the vitiligo marketing agency page.

Vertical 04 · Eczema

Paediatric + adult split · parent-buyer · steroid-safety framing

Eczema is two funnels — paediatric atopic dermatitis (parent-buyer, mother-as-researcher, WhatsApp intake, evening-hour consults) and adult atopic (self-buyer, dupilumab-era). Steroid-safety framing is the compliance edge that separates a credible dermatologist from the topical-steroid-abuse controversy. Chronic-care LTV runs Rs.40,000 to Rs.1.2 lakh. See the eczema marketing agency page.

Vertical 05 · Alopecia

Androgenetic vs alopecia areata · dermato-trichologist authority

Medical alopecia is the volume category the surgical hair transplant world ignores. Androgenetic alopecia (male and female) is the volume vertical; alopecia areata is the specialist vertical needing dermato-trichologist authority. PRP, minoxidil and finasteride live inside NMC Section 6 rules. The referral bridge to surgical hair transplant is a marketing choice, not an accident. See the alopecia marketing agency page and the hair transplant marketing agency pillar.

Vertical 06 · Fungal infection

Seasonal · low-ticket high-volume · same-day WhatsApp

Fungal is the "gateway" dermatology consult — low-ticket, high-volume, high-repeat, monsoon-seasonal, and the front door for new-patient acquisition in every other vertical. Same-day WhatsApp booking beats any funnel design. CPQL runs Rs.120 to Rs.280 for a Rs.800 to Rs.1,800 first consult. See the fungal infection marketing agency page.

Vertical 07 · Pigmentation

Melasma-heavy · seasonality · medical-aesthetic overlap

Pigmentation is India's most-searched dermatology sub-vertical. Melasma dominates because the Indian skin, climate and hormonal picture converges to produce it. Chemical peel content, Q-switched Nd:YAG and pico laser toning, and the post-Diwali and post-Holi enquiry spikes are the operational reality. This is where medical and aesthetic dermatology overlap most directly. See the pigmentation marketing agency page.

Vertical 08 · Rosacea

Under-diagnosed · long-decision cycle · patient education

Rosacea is severely under-diagnosed in India, which is both the marketing problem and the marketing opportunity. Differential-diagnosis content (rosacea versus acne versus lupus versus seborrheic dermatitis) is the education play. The 35 to 55 female buyer averages an 8 to 14 month journey to correct diagnosis. See the rosacea marketing agency page.

CPQL benchmark matrix

Eight-vertical CPQL matrix.
ICG portfolio data, rolling 12 months.

Vertical Market avg CPQL ICG portfolio CPQL Treatment LTV Best channel
AcneRs.220-Rs.600Rs.180-Rs.450Rs.12K-Rs.45K per treatment cycleMeta Reels + GBP
PsoriasisRs.900-Rs.2,400Rs.700-Rs.1,800Rs.60K-Rs.1.8L over 5-10 yrsSearch + GP referral
VitiligoRs.1,400-Rs.3,600Rs.1,100-Rs.2,800Rs.80K-Rs.3.5L per patientYouTube + Search
EczemaRs.400-Rs.1,100Rs.320-Rs.850Rs.40K-Rs.1.2L over 3-5 yrsSearch + WhatsApp
Alopecia (medical)Rs.600-Rs.1,600Rs.480-Rs.1,200Rs.35K-Rs.90K per yearMeta + Search
Fungal infectionRs.160-Rs.380Rs.120-Rs.280Rs.4K-Rs.12K per episodeGBP + WhatsApp
PigmentationRs.700-Rs.1,900Rs.560-Rs.1,450Rs.28K-Rs.85K per protocolMeta + Search + GBP
RosaceaRs.1,600-Rs.3,200Rs.1,300-Rs.2,600Rs.35K-Rs.1.1LSearch + YouTube

Source: ICG portfolio data, rolling 12 months (Sept 2025-Aug 2026), n=9 dermatology engagements across solo dermatologist and multi-branch chain models. Ranges vary by city, wave and creative maturity.

Compliance framework · dermatology

Compliance is where most agencies fail.

Aesthetic dermatology and clinical dermatology have different restriction profiles. ASCI notices spike in Q3/Q4 for cosmetic clinics; NMC enforces harder on medical-derma content. ICG runs both with separate compliance sub-workflows.

Primary law
NMC Ethics Code Section 6 + ASCI Code

No before-after images without DPDP consent + prominent disclaimer. No comparative "safer than" claims. No influencer endorsements without disclosure.

Penalty for violation
Enforcement bite

NMC suspension of practising licence + ASCI take-down orders

ICG approach
Compliance-first workflow

Every ad + landing page + email routed through a compliance checkpoint before publishing. Zero enforcement actions across 150+ healthcare clients since 2018.

Frameworks ICG operates under

NMC Ethics Code 2026 · DPDP Act 2023 · ART (Regulation) Act 2021 · NABH 6th Edition · Dental Council of India · Schedule J (drug advertising) · UCPMP 2024 · ASCI Healthcare Guidelines

Compliance interpretations current as of September 2026. Enforcement bulletins tracked weekly by ICG's compliance research desk. See our editorial standards for how we source and update these.

Two operating models

The dermatologist-founder practice
versus the skin-clinic chain.

The eight-vertical map is the same for both models; the operating rhythm is not. The solo-dermatologist practice and the multi-branch skin-clinic chain optimise for different variables, budget for different line items, and scale on different constraints. Mixing the two playbooks is where clinics stall.

Model 01 · Dermatologist-founder practice (Wave 1)

One doctor · one clinic · 6-18 patients a day

The Wave-1 dermatologist runs the practice, sees the patients, signs off the creative, and — for the first two years — is the brand. Marketing budget sits in the Rs.40,000 to Rs.1,00,000 per month band, split roughly 45 per cent to Meta Reels and boosted content, 25 per cent to Google Ads on high-intent condition queries, 15 per cent to content and SEO, 10 per cent to review-generation and GBP hygiene, 5 per cent to creator collaborations. The constraint is the doctor's chair-time. A well-run Wave 1 gets to 18 to 22 patients a day and the founder has to choose between a chair-multiplication move (associate) or a satellite move (second location).

The vertical mix at Wave 1 is fungal-anchored (walk-in volume + acquisition front door), acne-driven (Meta Reels + parent-buyer WhatsApp), and pigmentation-lifted (higher ATV, aesthetic overlap). Psoriasis, eczema, vitiligo, alopecia and rosacea are add-on verticals that build LTV rather than acquisition volume.

Model 02 · Multi-branch skin-clinic chain (Wave 2)

3-30+ branches · centralised brand · associate dermatologists

The Wave-2 chain is a different animal. The founding dermatologist becomes the clinical head; new-patient volume comes from a brand-level engine and gets routed to associate dermatologists across branches. Marketing spend jumps to Rs.2,00,000 to Rs.6,00,000 per month per five branches, and the split shifts: 30 per cent to Meta at brand-level, 25 per cent to Google Ads on brand and non-brand terms, 20 per cent to programmatic city-and-vertical landing pages, 15 per cent to central content authority, 10 per cent to central review and reputation infrastructure.

The chain constraint is not chair-time — it is brand consistency, reputation management across branches, and the discipline to avoid one associate dermatologist running rogue creative that fails NMC or ASCI at the brand level. GBP is per-branch (Google treats each physical location as a separate entity; roll-up to a corporate profile is a suspension risk), content is centralised, ads are centralised, review dashboards are centralised.

Content architecture

Condition-first content architecture.
Why "book an appointment" pages lose to "understanding your condition" hubs.

The dominant pattern in Indian dermatology marketing five years ago was a homepage plus a services grid plus a "book an appointment" form. It worked because paid search was cheap and organic discovery was thin. Both are gone. AI Overview answers commercial-intent queries with education content; Meta Reels rewards content that teaches over content that sells; the ChatGPT-native researcher will not book without first landing on a page that credibly explains the condition. The consequence is that "understanding your condition" hubs now outperform "book an appointment" pages on every metric that matters — organic sessions, session duration, WhatsApp intake, consult booking and CPQL.

The condition-first architecture that consistently wins across our portfolio has four layers. Layer one is the condition hub — a single deep page for each vertical (acne, psoriasis, vitiligo, eczema, alopecia, fungal, pigmentation, rosacea) that treats the reader as an adult trying to understand what is happening to them, not as a lead to be captured. Layer two is a set of condition-specific spokes — differential-diagnosis content, treatment-option content, cost-band content, recovery-and-follow-up content — that rank on long-tail queries and refer back to the hub. Layer three is the city-and-vertical page — the acne page for Delhi, the vitiligo page for Chennai — that carries locality-specific trust signals (branch list, empanelments, local-language elements). Layer four is the operator-guide long-form (the "how a clinic scales" and "cost benchmarks" pages) that captures the founder-doctor researcher deciding whether to hire an agency.

The compliance overlay across every layer is the same. Every condition hub, every spoke, every city page carries a named-author byline with credentials and photograph, an FAQPage schema block, an Article schema block with dateModified, an evidence citation or two where a specific claim is made, and a WhatsApp CTA that sits after the education not before it.

Retention economics

The retention economics of chronic-care dermatology.
Why the LTV curve dwarfs the acquisition curve.

The single most under-modelled variable in Indian dermatology marketing is patient LTV. Practices budget acquisition against a first-consult value of Rs.800 to Rs.3,500 and cap their marketing spend accordingly. They miss that the same patient — properly retained — carries a lifetime value ten to sixty times higher, spread over follow-ups, refills, seasonal flare visits, family-member conversions, and cross-vertical treatment. A psoriasis patient managed well is a Rs.60,000 to Rs.1.8 lakh relationship over five to ten years, produces two to four family-member referrals, and drops a review that lifts the local pack ranking for every future acne enquiry.

The retention SOP that captures this LTV is not glamorous. It is a refill-window reminder cadence on WhatsApp (day 25, day 55, day 85 for a monthly refill), a seasonal flare-management campaign in winter (psoriasis and eczema) and monsoon (fungal and pigmentation), a post-treatment satisfaction check at day 30 and day 90, an annual review nudge for chronic patients who have not booked in six months, and a teleconsult adjacency for out-of-station follow-ups. None of this looks like marketing. All of it is the marketing that matters.

The unit economics resolve differently once retention is priced in. A Wave-1 practice spending Rs.60,000 per month on acquisition and running a disciplined retention SOP can compound to a Rs.90 lakh to Rs.1.4 crore annual clinical revenue book inside 24 months. The same practice spending the same amount on acquisition without a retention SOP tops out around Rs.55 to Rs.75 lakh. The compounding is entirely retention-driven.

Wave 1 to Wave 2

The Wave-1 (solo doctor) to Wave-2 (chain) growth path.
The three decisions that determine whether the chain compounds or dilutes.

The transition from Wave 1 to Wave 2 is where most dermatology practices lose their marketing engine. The founder-doctor who compounded a solo clinic to 20 patients a day suddenly cannot compound the same model across four branches with associate dermatologists. Three decisions determine whether the chain compounds or dilutes brand equity.

Decision one — brand versus branch topology. A brand-level primary site with programmatic branch pages consolidates search equity and scales content authority; separate branch sites fragment equity and require rewriting content per branch. The compounding chains we have worked with pick the brand-level model early — every new branch is a programmatic page, not a new domain. The chains that fragment usually did it because a partner acquisition brought an existing site along and nobody made the migration call.

Decision two — associate dermatologist creative governance. Associate dermatologists want to build personal brands. Chains that let five associates each run their own Instagram end up with five under-nourished handles and a diluted brand voice. The pattern that works is one brand-level handle producing brand-voice content plus surgeon-authority Reels featuring individual associates who are named and credited but not brand-primary. The associate builds authority; the brand keeps compound.

Decision three — retention SOP transfer. The founder-doctor's retention discipline in Wave 1 was informal — the founder remembered the patient. In Wave 2 that memory has to become a CRM, a WhatsApp automation, a follow-up SOP that every branch executes identically. Chains that make this transfer explicit in the first six months of the second branch's operation compound. Chains that do not lose 30 to 50 per cent of the LTV they earned in Wave 1.

AI Overview + ChatGPT for skin

AI Overview and ChatGPT visibility
for skin-condition queries.

The dermatology category is one of the most AI-Overview-dominant in Indian healthcare search. A 24-year-old typing "how to treat acne scars" into Google now sees three AI Overview paragraphs above the organic listings, and the sources cited are the clinics whose content is structured to be extractable. The same patient often opens ChatGPT and asks a similar question before ever seeing a Google result. The clinics that appear in these answers earn a trust anchor no ad placement can match; the ones that do not effectively disappear from the top of the funnel.

The Answer Engine Optimisation work — AEO — for dermatology has four practical moves. First, structure every condition page for extraction: a plain-language definition sentence at the top of each concept, followed by a bulleted or numbered elaboration, followed by a longer discussion. Second, mirror headings to the questions patients type ("What causes melasma to darken after Diwali?" outperforms "Melasma seasonality" as an H2). Third, publish FAQPage schema with well-written question-and-answer blocks. Fourth, use named-author bylines with credentials, photograph and a linked biography page — author authority is now weighted meaningfully in AI Overview citation selection.

The measurement problem is real. AI Overview citations are not directly measurable in GSC yet; ChatGPT citations are not measurable at all. Track proxy signals: the ranking of AEO-optimised pages on long-tail question queries, the share of "no click" impressions in GSC, and the "how did you hear about us" enquiry-form field with ChatGPT and AI Overview as explicit options.

90-day activation + 12-month calendar

90-day activation timeline
and 12-month editorial calendar.

A well-scoped medical dermatology marketing engagement moves in three 30-day sprints and settles into a rhythm by month four.

Day 0 to Day 30 — Foundation. Audit the practice's current digital footprint: GBP health score, existing website content depth, current Meta and Google Ads structure if any, review counts, and current CPQL by vertical. Build the compliance rulebook (NMC + ASCI + Meta Personal Attributes) with the founder-doctor's sign-off. Publish the priority condition hub — usually acne for a Wave-1 practice, psoriasis or vitiligo for a chronic-care-heavy practice. Claim and optimise all GBP profiles. Wire WhatsApp intake to a shared inbox. Launch the review-generation SOP.

Day 30 to Day 60 — Optimisation. First Meta creative batch clears review at the target volume (10 to 15 creative variants per week for a Wave-1 acne-primary practice). Google Ads shifts to target CPA if conversion volume clears the 30-in-30 threshold; otherwise refine keyword lists while staying on manual CPC. Publish two more condition hubs on the vertical mix priority list. Set up refill-window WhatsApp automation for the chronic verticals.

Day 60 to Day 90 — Scale. Meta Reels cadence lands at target (four to six per week for acne-primary, two to three per week for chronic-heavy). Google Ads expanded to phrase-match research layer. First long-form YouTube for vitiligo, psoriasis or eczema goes live. Review count on trajectory (60-plus new reviews in the quarter for a mid-size clinic). CPQL trending into the target range across the two or three priority verticals.

Month 4 to Month 12 — Editorial calendar. A rolling 12-month plan built around the specific vertical mix. For a Wave-1 dermatology-founder practice with acne, pigmentation, fungal and eczema services, a working monthly cadence: two condition-hub deep updates per month (rotating verticals), four to six Meta Reels per week (rotating hooks, avoiding Personal Attributes triggers), one monthly YouTube long-form on the chronic vertical mix, monthly refresh of the seasonal creative (winter psoriasis/eczema, monsoon fungal/pigmentation, post-festival pigmentation), and a quarterly review of GBP performance, ranking on priority queries, and retention SOP execution.

CPQL benchmarks · ICG vs market

38–58% lower CPQL
in 90 days. Across every specialty.

Most dermatology marketing agency india pitches sell on CPL. ICG sells on CPQL — Cost Per Qualified Lead — the cost of a lead that actually shows up for a consultation. The difference is often 3–4×. Here is what our 150+ healthcare clients actually pay.

Specialty Market avg CPQL ICG avg CPQL ICG reduction
IVF & Fertility₹2,400₹1,180−51%
Aesthetic Dermatology₹1,950₹1,020−48%
Plastic Surgery₹3,600₹2,050−43%
Hair Transplant₹4,300₹2,280−47%
Ophthalmology (LASIK / cataract)₹1,700₹720−58%
Mental Health (psychiatry / therapy)₹2,200₹1,310−40%
Dental (chains)₹980₹540−45%

90-day averages from ICG's live portfolio across Delhi NCR, Mumbai, Bangalore, Hyderabad, Pune, Chennai, and tier-2 cities. Adjust for city: metro CPQLs run 20–35% higher than tier-2 across all specialties.

HealthApex OS · The proprietary stack

Eight platforms. One intelligence layer.

Nexus CRM healthcare lead management · Beacon attribution · Hawk CRM intelligence · Phoenix clinic revenue · HealthPro 360 PMS · YODA YouTube intelligence · Agency OS live reporting · AIO Intel AEO+LLM citation tracking. Built in-house since 2018 — included in every dermatology marketing agency india engagement.

Explore HealthApex OS See all eight platforms in detail
Two products worth knowing

Hawk and YODA.
Standalone offers built for specific gaps.

⏵ Hawk · CRM Intelligence

Is your CRM hiding what it should be showing?

Hawk shows where your leads are leaking: which went cold, which were downgraded by automation, which are recoverable. Free Lead-Leak Audit in 48 hours.

Explore Hawk + free audit →
▶ YODA · YouTube Intelligence

Is your YouTube channel generating patients, or just views?

YODA connects YouTube content to consultation bookings. Patient testimonial videos generate 6.9× more consultations per view than condition explainers.

Explore YODA →
The diagnostic framework

Most healthcare marketing agencies treat symptoms.
ICG diagnoses root causes.

High CPL. Junk leads. Low ROAS. These are symptoms, not problems. ICG's diagnostic framework — built across 150+ healthcare engagements — maps every symptom to its actual root cause and the specific treatment that fixes it.

Symptom Diagnosis ICG Treatment
High CPL across all campaignsPoor channel selectionSLC Matrix
Leads come in, but most are junkInefficient digital operationsDCG Matrix
Leads convert to appointments slowlySales process / telecaller gapsACE Matrix + MIS Tool
CPL keeps rising every monthCross-firing between ad groupsN-Gram + Cross-Firing Analysis
Meta Smart Bidding not optimisingEMQ at 2.5, no first-party signalBeacon CAPI middleware
Traffic is up but enquiries flatWrong T-1 page; no CRODevice ID Tool + OHMRC Model
Invisible to ChatGPT / AI OverviewsNo AEO infrastructureAIO Intel Tool + cluster architecture
Patient database underutilisedNo retention motion on existing patientsPhoenix revenue intelligence
Can't see which leads are leaking from your CRMNo CRM intelligence layer; backward movement invisibleHawk · CRM intelligence + Lead-Leak Audit
YouTube channel has subscribers but no patientsOptimising for views instead of consultation attributionYODA · YouTube intelligence + consultation attribution

Every framework in this table is proprietary to ICG. Calibrated across 150+ live healthcare accounts since 2018. Full ICG methodology → · Glossary →

Complete guides

Read the complete guide
for your category.

Six pillar guides — each 8,000–15,000 words of original ICG methodology, CPQL benchmarks, and live client data. The depth no other Indian healthcare marketing agency publishes.

Healthcare Marketing India — Complete Guide → Doctor Marketing India — Complete Guide → Hospital Marketing India — Complete Guide → IVF Marketing India — Complete Guide → Healthcare Performance Marketing — Complete Guide → Healthcare SEO + AEO India — Complete Guide →

More insights at ichelonconsulting.com/insights · 250+ articles · all healthcare-only

Case study snapshots

Anonymised engagement outcomes
from ICG dermatology portfolio.

Solo dermatologist practice · West Delhi

Situation: Single-doctor practice, mixed medical and aesthetic caseload, 9 to 12 patients a day at plateau for 14 months. CPQL Rs.640 blended across verticals. GBP health score 62 out of 100. Meta ads paused for six months after repeated Personal Attributes rejections.

Diagnosis: No compliance rulebook for creative production; every Meta batch was rewritten from scratch, half got rejected. Condition-hub content thin — one 800-word services page across four verticals. Retention SOP absent.

Intervention: Wrote the three-regulator rulebook and rebuilt 22 Meta creative variants against it. Published acne, pigmentation and fungal condition hubs (2,200 to 2,600 words each) with named byline and FAQPage schema. Wired WhatsApp refill-window automation. Rebuilt GBP with correct primary category and empanelment attributes.

Result: Meta creative approval rate 47 per cent to 91 per cent. CPQL Rs.640 to Rs.310 at month five. Patient volume 9-12 to 22-26 per day at month nine. Review count 84 to 218 at 4.7 star average. (ICG internal data, 2026.)

4-branch skin-clinic chain · North India

Situation: Four-branch chain built through one greenfield and three regional acquisitions. Four independent websites, four unmanaged GBP profiles, three legacy Meta ad accounts. Blended CPQL Rs.980 across acne, pigmentation and fungal. Two acquired-brand domains still ranked but did not redirect to the chain brand.

Diagnosis: Fragmented brand architecture bleeding search equity. Reviews scattered with no central-response cadence; negative reviews sat 20-plus days unanswered. No shared content authority; each branch site had four to six thin pages.

Intervention: Migrated to brand-level primary site with four programmatic branch pages. 301 redirects preserved acquired-brand equity. Built central condition-hub library (acne, pigmentation, fungal, eczema, psoriasis). Each branch page overlays locality: branch dermatologist list, empanelments, local-language creative. Central review-management dashboard with one-hour negative-review alert. Meta ads consolidated to a brand-level account with four geo-targeted campaigns.

Result: Blended CPQL Rs.980 to Rs.440 at month six. Combined organic sessions plus 210 per cent by month nine. Consolidated GBP review base 260 to 720 at 4.6 to 4.7 star average across branches. Two subsequent greenfield branches hit break-even inside 100 days versus a pre-consolidation chain average of 160 to 200 days. (ICG internal data, 2026.)

Dermato-trichology practice · Bangalore

Situation: Two-consultant dermato-trichology practice, alopecia-heavy caseload, strong clinical reputation among referring GPs but a referral-only new-patient pipeline that had flattened. Digital footprint: static website, dormant Instagram, no GBP optimisation, no medical-alopecia content.

Diagnosis: "Androgenetic alopecia dermatologist Bangalore" search intent was contested by hair transplant chains, not by dermato-trichologists. The practice had no content authority on the medical-alopecia versus surgical-hair-transplant boundary. No content differentiated dermato-trichology from generic dermatology.

Intervention: Built the medical-alopecia content hub with androgenetic alopecia, alopecia areata, dermato-trichologist-authority and PRP compliance-safe pages. Positioned the practice as the medical-first alternative to surgical hair transplant, with an appropriate-referral pathway to surgical partners for candidates who genuinely needed FUE. Launched surgeon-led Instagram content on scalp-diagnostic craft. Wired GBP with correct sub-specialty positioning.

Result: New-patient consultations from digital 6 to 48 per month at month six. "Androgenetic alopecia dermatologist Bangalore" top-3 organic at month eight. Referral share of new patients maintained while direct-search share grew from 8 to 34 per cent. (ICG internal data, 2026.)

YouTube Marketing · ICG YODA Intelligence

Healthcare YouTube in India: a 180M-view market clinics barely contest.

Across 13 doctor + clinic channels ICG manages, 180.3M lifetime views drove patient acquisition in 9 specialties. The clinics that move now — with data instead of guesswork — can own their specialty's search authority before it's contested.

Lifetime views (ICG dataset)
180.3M
Channels analysed
13
Specialties covered
9
Read the State of Doctor YouTube India 2026 (flagship) → Explore ICG's YouTube Marketing service →
Frequently asked

About dermatology marketing
agencies in India.

The band depends on the vertical mix. Fungal-heavy general dermatology: Rs.180 to Rs.400 blended. Acne-primary Wave-1 clinic: Rs.220 to Rs.500. Chronic-care-heavy practice (psoriasis, eczema, vitiligo weighted): Rs.700 to Rs.1,800. Chain-scale Wave-2 operator across a mix of five to eight verticals: Rs.400 to Rs.900 blended. The dominant driver of efficiency is not budget but creative compliance discipline — clinics with a documented NMC + ASCI + Meta Personal Attributes rulebook run CPQL 30 to 50 per cent lower than clinics without one.

Different buyer, different decision surface, different LTV curve. Medical dermatology sells expertise and clinical infrastructure to a patient managing a condition — trust, evidence, chronic-care retention. Aesthetic dermatology sells price-transparent discretionary treatments to a lifestyle buyer — Instagram inspiration, brand aesthetic, before-and-after craft. The marketing stacks share vocabulary but almost nothing operationally. A clinic running both should treat them as two funnels with two landing-page stacks, two ad accounts (or two campaign structures inside one account), and two content plans — not one merged story.

The categories that consistently trigger Personal Attributes rejection: acne (any hook implying the viewer has acne), pigmentation and melasma (any hook implying the viewer has dark spots), hair loss (any hook implying the viewer is thinning), and vitiligo (any hook implying the viewer has patches). The compliant frame is condition-education without implying viewer state — 'Learn about acne treatment options' passes; 'Struggling with acne? Book a consult' does not. In our portfolio, first-time dermatology creative from an unfamiliar team clears review at roughly 55 to 60 per cent; a team briefed on the rulebook clears at 88 to 94 per cent.

NMC Section 6 prohibits before-and-after imagery used as an advertising claim by a registered medical practitioner. In-clinic before-and-after documentation for medical record purposes is permitted; showing the same imagery in ads, on the homepage as a testimonial-style claim, or on Instagram as a promotional carousel is not. The compliant public-facing frame is educational — surgeon on camera explaining the treatment protocol, technology, and typical clinical trajectory without imagery that implies a specific outcome for the viewer. Compliance boundaries do shift; the pragmatic move is to build the content library on the conservative interpretation.

Fungal is the fastest to activate and the highest-volume front door. Same-day WhatsApp booking, low ticket, monsoon seasonality, walk-in-adjacent — a new clinic can start seeing fungal enquiries inside a week of launching GBP and paid search. Acne is the second-fastest — Meta Reels build awareness in three to six weeks — but requires the compliance rulebook to be in place first. Pigmentation is the slowest of the three to activate but carries the highest ATV. The Wave-1 sequencing we recommend is fungal for volume, acne for scale, pigmentation for lift.

Within a Rs.40,000 to Rs.1,00,000 monthly Wave-1 budget: 40 to 50 per cent to Meta (Reels + boosted content), 20 to 30 per cent to Google Ads on high-intent condition queries, 12 to 18 per cent to content and SEO retainer, 8 to 12 per cent to review-generation and GBP hygiene, 3 to 6 per cent to creator collaborations. The proportions shift with vertical mix — a psoriasis or vitiligo-primary practice moves 10 to 15 percentage points from Meta to search and YouTube; a fungal-anchored general dermatology practice moves 5 to 10 points from Meta to GBP and local citation.

For chronic-care verticals — psoriasis, eczema, alopecia — teleconsult meaningfully extends the LTV curve by 20 to 35 per cent because refill and flare-management visits that used to lapse now happen. For acne, pigmentation and fungal, teleconsult is neutral to marginally positive — the physical-exam requirement caps the shift. Teleconsult is not a growth channel in itself; it is a retention multiplier for the chronic verticals.

A chain engagement centralises three things and localises two. Centralised: brand-level primary site with programmatic branch pages, content authority (condition hubs and cost benchmarks), and review-management dashboard. Localised: each branch has its own GBP profile with locality-specific attributes (empanelments, language, hours), and each branch page overlays local-language creative and dermatologist bios. Ad accounts stay centralised with per-branch geo-targeted campaigns. This lets a seventh branch launch mean one new page, not 25 new content pieces.

For a Wave-1 dermatologist-founder practice starting from a low base: 60 to 90 days to see the first meaningful CPQL shift, four to six months to build a compounding content and reviews engine, nine to twelve months to reach a stable 20-to-30-patients-a-day operating rhythm. Chains take longer to initial ROI because the branch integration work absorbs the first 90 days, but they compound faster once the central engine is live — typically hitting break-even on additional branches inside 90 to 120 days versus 150-plus for pre-consolidation chain launches.

The single biggest failure mode we see is treating dermatology as one funnel. Clinics run one landing page across eight condition verticals, one Meta ad set with generic 'skin problems' hooks, one Instagram grid that alternates acne posts with pigmentation posts with hair-loss posts. Every element under-performs because none of them speak to a specific buyer. The category needs the eight-vertical split written into the site architecture, the ad account structure and the content calendar. The clinics that make that split compound; the clinics that do not stall around 12 to 15 patients a day and blame the platforms.

The ICG technology stack

Nine tools. One compounding system. HealthApex OS
Built in-house. Deployed in every engagement.

ICG's results are reproducible because they are built on proprietary infrastructure — not agency intuition or generic tools. These nine HealthApex OS platforms are what power every ICG engagement.

Healthcare CRM

Nexus CRM

Healthcare CRM & Lead Management

ICG's healthcare-specific CRM and lead management system. Specialty-configured funnel stages for IVF, dental, aesthetic, ortho, hospital OPD. 1-click CAPI + GCLID via Beacon. Hawk intelligence built in. DPDP-compliant by architecture. Deployed across 300+ healthcare centres.

  • Specialty-specific funnel stages, not generic SaaS pipeline
  • 1-click CAPI + GCLID via Beacon attribution
  • Telecaller leaderboard + adherence scoring native
  • DPDP Act 2023 compliant by architecture
Explore Nexus CRM →
Business Layer

Hawk

CRM Intelligence & Lead-Ops MIS

Sits as the business intelligence layer above your CRM — Nexus, Salesforce, LeadSquared, HubSpot, Zoho, or any custom CRM. Shows where leads are leaking, which effort is wasted, and which good leads were quietly downgraded by automation — not by a human decision.

  • Sits above your existing LMS — no replacement
  • 83% of effort goes to dead leads — surfaced Day 1
  • ~75% qualified-lead downgrades by automation
  • Free Lead-Leak Audit in 48 hours
Explore Hawk + free audit →
Attribution Core

Beacon

Attribution Engine & CAPI Middleware

Sits at the centre of every ICG attribution architecture. CAPI middleware connecting Meta Ads, Google Ads, WhatsApp and IVR to your CRM. Lifts Event Match Quality from 2.5 to 6+, reducing CPM 30–40% from the same budget.

  • Server-side CAPI — bypasses iOS privacy changes
  • EMQ 2.5 → 6+ across portfolio
  • 30–40% CPM reduction from EMQ lift alone
  • Multi-touch: ad → consultation → revenue
Explore Beacon →
Practice Management

HealthPro 360

PMS with built-in revenue intelligence layer

The only PMS that tracks cross-sell and up-sell opportunities within your existing patient base. 12 modules covering OPD, IPD, Pharmacy, Labs, Billing, Inventory, Patient Portal, Smart Scheduling, RBAC, AES-256 encrypted storage.

  • Only PMS with built-in Revenue Intelligence
  • Cross-sell signal tracking within existing patients
  • 12 modules: OPD, IPD, Pharmacy, Labs, Billing+
  • Audit trails + RBAC + AES-256 encryption
Explore HealthPro 360 →
Revenue Layer

Phoenix

Revenue intelligence built over your existing PMS

If you already have a PMS — Akhil Systems, Practo, or any other — Phoenix builds the business intelligence layer on top of it without replacement. Currently live across 46 centres for a national chain.

  • Works over your existing PMS — no migration
  • Daily action queue: Prevent Loss / Maintain / Grow
  • Catches unbilled services, collection gaps, lapsing patients
  • CPQL variance ₹620–₹3,800 → ₹680–₹1,420
Explore Phoenix →
YouTube Intelligence

YODA

YouTube analytics that measures patients, not views

The only YouTube intelligence platform built for healthcare business outcomes. Connects video performance to actual consultation bookings — not views, not subscribers. Patient testimonial videos generate 6.9× more consultations per view than condition explainers.

  • Consultation attribution per video — not views
  • Demand-gap: what patients search that your channel misses
  • 50+ doctor channels tracked across India
  • AIO readiness scoring: which videos AI tools cite
Explore YODA →
Governance & Transparency

Agency OS

Full transparency. Instant diagnosis. Zero surprises.

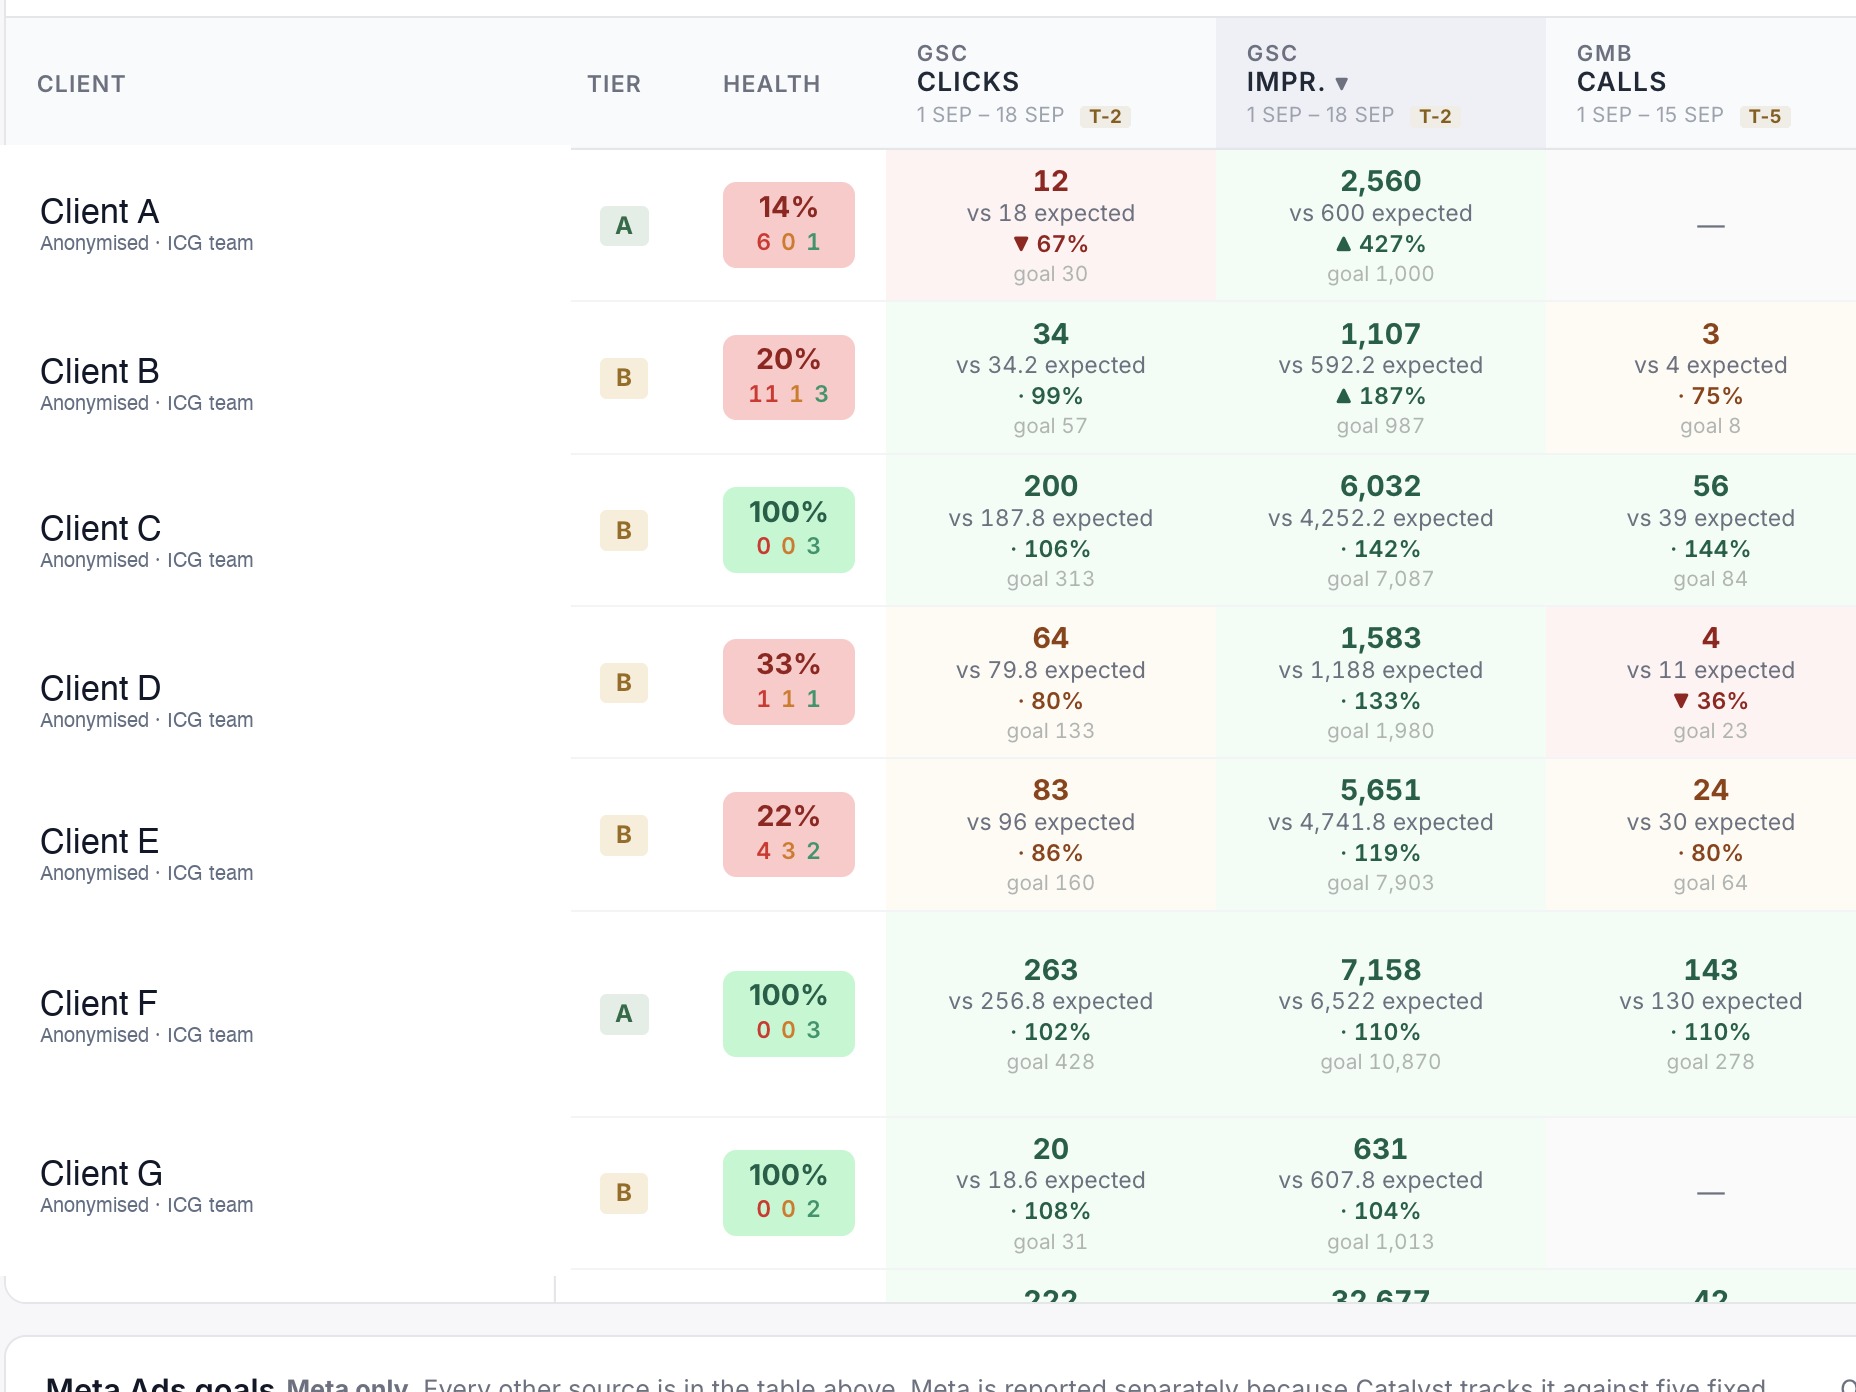
ICG's centralised governance platform — every client sees everything in real time, and ICG's team sees every problem the moment it surfaces. 30+ real-time alert systems fire the moment a metric drifts outside its performance envelope.

  • GSC, GA4, Google Ads, Meta Ads, IVR — one live view
  • 30+ real-time alert systems per account
  • CPQL drift alert at >15% week-on-week change
  • Client login: full transparency on your account
Explore Agency OS →
AEO & LLM Intelligence

AIO Intel

AI Overview + LLM citation tracking, healthcare-tuned

Knows the moment ChatGPT, Perplexity, Google AI Overviews and Gemini cite your brand in patient answers — and which content drove the citation. Bot-aware dashboard with GA4-registered custom dims (AIO source, AIO referrer) and IndexNow + GSC API integration.

  • Live tracking across ChatGPT / Perplexity / Google AIO / Gemini
  • Bot-aware: knows human vs scraper traffic
  • Custom GA4 dims register AIO source + referrer
  • IndexNow + GSC API: content surfaced to LLMs within hours
View AIO Intel dashboard →
Competitor Intelligence

Prism Spy

Every Meta + Google ad your competitors run, watched daily

Tracks 75+ Indian healthcare brands, 2,150+ active ads, ₹50Cr+ aggregate ad spend visibility per month. Surfaces what's working, what's been killed, what offers are emerging. Powers every ICG Meta Ads brief, Performance Marketing diagnostic, and IVF / derm / dental specialty campaign with real competitive intelligence.

  • 75+ brands tracked across 30+ healthcare specialties
  • 2,150+ active ads · daily refresh
  • Activity Feed: every spend / hook / pause logged
  • Offers Intelligence: 250+ offers in market tracked
Explore Prism Spy →
GBP Intelligence Platform

Angryturtle

Every Google Business Profile scored, tracked, protected, and grown from one command centre

ICG's proprietary Google Business Profile intelligence platform. Scores every listing across 7 dimensions, tracks rank on a live geo-grid across your actual service area, audits NAP + citations, monitors 531 suspension-risk factors continuously, and drafts Google Posts on cadence. Currently managing 143 healthcare listings with 0 suspensions and 4.76★ portfolio average across 28,137 reviews.

  • 143 listings under management · 0 suspensions · 4.76★
  • 7-dimension Health Score + 5-factor Rank OS per listing
  • Geo-grid rank tracking + NAP + Citation audit + Profile Shield
  • NMC + NABH + ART Act + DPDP compliance built into every content + review workflow
Explore Angryturtle →

Every ICG engagement runs on some combination of these ten HealthApex OS tools. The diagnostic determines which combination is right for your practice.

Explore HealthApex OS → See the full stack live on your account — free 30-min audit
The team behind your account

Every diagnostic is led by a founder.
You'll know their names before the engagement begins.

ICG was built by three IIT BHU engineers who entered healthcare marketing with a specific intent: to build the tools that didn't exist and run the campaigns that most agencies couldn't. When you book a diagnostic, Rohit or Abhash leads it personally. Not an account manager. Not a senior executive. The people who built what you're evaluating.

The ICG team — 60+ healthcare marketing specialists at Gurgaon HQ

60+ specialists.
One growth engine.

Performance marketers, analysts, AI engineers, content strategists, and operations specialists — all healthcare-only. Headquartered in Gurgaon since 2018.

Rohit Gupta — Leader, ICG

Rohit Gupta

Business & Growth Lead & Director

IIT BHU · IIM Rohtak

Rohit's first question in every diagnostic: "When you ask your agency why patients aren't booking — what do they say?" He says the answer tells him more than any dashboard.

Full profile →
Abhash Kumar — Leader, ICG

Abhash Kumar

Strategy & Analytics Lead & Director

IIT BHU · IIM Bangalore

Abhash built Beacon because most agencies couldn't answer one question: "Which of my campaigns generated that consultation?" He decided the problem was solvable in code. It was.

Full profile →
Deep Das — Leader, ICG

Deep Das

Technology & AI Lead & Director

IIT BHU

Deep built the 4-Bot patient lifecycle system after watching a client lose 60+ qualified leads in one week to a 6-hour WhatsApp response window. He decided the problem was solvable in code. It was.

Full profile →
HealthApex OS Pricing · All-Inclusive · Billed Annually
₹2,999 – 3,999/month
Single Tool
Hawk CRM intelligence overlay (₹2,999), Nexus CRM / HealthPro 360 / Phoenix alone (₹3,999 each).
₹4,999 – 11,999/month
Bundled Suite
Nexus + Hawk ₹4,999. HealthPro 360 + Patient Portal ₹7,999. Operations Suite (HealthPro + Phoenix + Portal) ₹11,999.
₹14,999/month
Complete HealthApex OS ★
All 8 tools: Nexus + Hawk + Beacon + Phoenix + HealthPro 360 + YODA + Agency OS + AIO Intel. Best value. Full integration.

Transparent. Billed annually. No hidden integration fees. Most Indian clinics save 60-80% vs Salesforce Health Cloud (₹3L+/month) or a 5-vendor multi-tool stack. Complete HealthApex OS at ₹14,999/month is 40-60% cheaper than maintaining a multi-vendor stack — plus you get unified data, one compliance officer, one founder-led engagement. Enterprise tier (hospital networks, multi-brand, custom modules): ₹50,000 – ₹3,00,000/month, founder-led.

Book the free 30-min diagnostic →
Selected ICG clients

Healthcare brands ICG
has worked with.

A representative slice of the 300+ healthcare brands ICG has delivered for across India. Full client list available under NDA during a Brand and Growth Diagnostic.

Read full client case studies →

Sources & methodology
View sources cited on this page
  • Indian Association of Dermatologists, Venereologists and Leprologists (IADVL) clinical guidelines
  • NMC Professional Conduct Regulations 2002, Section 6 — advertising by medical practitioners
  • ASCI Code — Chapter III (misleading claims) and healthcare guidelines
  • Meta advertising standards — Personal Attributes policy
  • ICG portfolio data (n=9 dermatology engagements, Sept 2025-Aug 2026)

Ready to build a
medical dermatology marketing engine?

Start with a complimentary 30-minute Dermatology Growth Diagnostic from ICG. For dermatologist-founder practices, dermato-trichology clinics and multi-branch skin-clinic chains across India.

Chat with a Co-Founder
🎯 Goal-linked · Fixed + Goal-based Variable Pay · 19-mo retention
Chat with a Co-Founder