Healthcare Pharma & Life Sciences Other Industries
All Services Performance Marketing ChatGPT Ads India · NEW Social Media Marketing SEO & AEO / LLM YouTube Marketing LLM Optimization Brand & Growth Consulting AI Solutions Industries We Serve
Enterprise Hub · All Solutions + Services Growth Transformation AI Transformation Revenue Operations Fractional CGO Growth Operating System Executive Growth Advisory
Clinic Launch Programme (Hub) NABH Consulting India Healthcare Brand Launch Clinic SOP Creation Logo Design (Healthcare) Brand Book Creation Clinic Launch Marketing D2C Brand Launch Clinic Interior Design
Workforce Hub For Employers — post a requirement For Professionals — register Public Openings Training Academy AI Training Flagship
Hawk · CRM Intelligence (NEW) YODA · YouTube Intelligence Angryturtle · GBP Intelligence (NEW) Prism Pulse · Instagram Analytics (NEW) Beacon · Attribution Agency OS · Dashboards Phoenix · Clinic Revenue HealthPro 360 · PMS/HMS AI Patient Lifecycle Bots AI Lead Management System Smart Appointment System Healthcare CRM Patient Feedback System AI, Analytics & Automation Digital Transformation Calculators Free Digital Health Audit →
All 13 calculators → 🎯 Business Exploration Matrix (New) Dental Clinic Setup IVF Clinic + Lab Setup Multi-Specialty Hospital Setup Aesthetic / Cosmetology Clinic Dermatology Clinic Setup Generic Clinic Setup Physiotherapy Clinic Setup Diagnostic Centre Setup CAC Calculator CPQL Calculator Franchise ROI Calculator Revenue Leakage Calculator CRM ROI Calculator
All Events Workshop 1 · Jun 13 · AI in Clinical Practice Workshop 2 · Jun 27–28 · AI in Growth & Governance Hospital Ops Workshop · Jul 12 Pre-Summit Seminar · Aug 16 Grand Summit 2.0 · Oct 10–11 Bihar AI Summit · Recap AI Innovation Awards · Aug 22 Grand Summit 2.0 · Oct 2026 Aarambh 2026 Recap
Case Studies Insights & Blog Research Reports Calculators AI in Healthcare Digest
Our Story Leaders @ Ichelon · IN · US · AU Ichelon India · Gurgaon Ichelon Global · Dallas, TX Ichelon Australia · Sydney Speakers & Panelists Client Elevation Programme 🤝 Partner Connect 🇦🇪 ICG UAE Careers
Book a Growth Diagnostic
We Do It Right. The right diagnosis. The right strategy. The right systems. Giving healthcare leaders the confidence to make better decisions, build stronger operations, and achieve sustainable growth. — Team Ichelon
Trusted by 150+ healthcare & life-sciences brands
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Johnson & Johnson
Mankind Pharma
Adonis Phyto
Narang Biotec
Medanta
Redcliffe Labs
Sitaram Bhartia
Metro Hospitals
Tulasi Hospital
Bloom IVF
Milann
Prime IVF
MedLinks
Handa
Bhardwaj
Eye Q
Alopecia Marketing · India · 2026 Playbook

Alopecia Marketing
Agency in India.

By Rohit Gupta · Business & Growth Lead, Ichelon Consulting Group. Reviewed by Hanuman Sihag, SEO Reviewer. Updated September 2026.

Medical alopecia is the volume category the surgical hair transplant world does not target directly. Androgenetic alopecia — male and female pattern — is the volume vertical, and alopecia areata is the specialist vertical that needs dermato-trichologist authority. Both sit alongside surgical hair transplant but do not compete with it. This is the operator manual for the medical-first alopecia practice, including the referral bridge to surgical partners for the minority of patients who genuinely need FUE.

The ICG engagement model
Every practice welcome — packages from ₹20,000/mo.
Goal-linked packages · Fixed retainer + Goal-based Variable Pay · 19-month average client retention — industry-leading. Read the full engagement model →
{-- Agency OS thumbnail · 2026-09-20 --}
Backed by App\Support\NamedExperts::get(). --}}
Medical vs surgical alopecia

Where the two funnels diverge.
Why they should be positioned as complementary.

The Indian hair-loss market has been dominated in advertising volume by surgical hair transplant chains — FUE, DHI, sapphire-blade positioning — for a decade. The consequence: a 32-year-old male experiencing early androgenetic alopecia now assumes hair transplant is the primary answer, when in fact the majority of early-stage AGA patients are better served by medical management (minoxidil, finasteride, sometimes PRP) for two to five years before any surgical consideration.

The dermato-trichologist practice that positions itself as the medical-first alternative to surgical hair transplant occupies a genuine gap in the market. The positioning is not adversarial to surgical partners — it is the appropriate-referral partner for the surgical route when a candidate genuinely needs it. The content architecture should make this dual model explicit: medical-first for stages I to III on the Norwood scale, surgical consideration for stages IV to VII when medical management has stabilised the residual hair, and a formal referral bridge for the patients who move between the two.

The hair transplant marketing agency pillar covers the surgical side. This page covers the medical side and the referral bridge.

Androgenetic alopecia

Male and female pattern — the volume vertical.
The dermato-trichologist funnel.

Androgenetic alopecia (AGA) — male-pattern and female-pattern hair loss — is the highest-volume medical alopecia sub-category. The male AGA buyer is 24 to 45, noticing thinning at the temples or crown, often after a barber, family member or partner has flagged it. The female AGA buyer is 28 to 55, noticing widening of the parting or increased shedding after post-partum, thyroid, or peri-menopausal transitions. Both are digitally active, both have researched extensively on ChatGPT and YouTube before the first enquiry, and both are cautious about the surgical hair-transplant advertising they have been exposed to.

The content architecture that consistently earns organic ranking and converts to consult: a hub page on androgenetic alopecia (types, staging, diagnostic approach, treatment ladder), a spoke on male pattern hair loss with Norwood-scale-aware content, a spoke on female pattern hair loss with Ludwig-scale-aware content, a spoke on medical management (minoxidil topical and oral, finasteride oral and topical, dutasteride, spironolactone for female), a spoke on PRP, and a spoke on when surgical hair transplant becomes appropriate. Each page named-authored by a dermato-trichologist with credentials, photograph and biography.

The compliance frame for AGA content: never guarantee regrowth, never publish before-and-after imagery as advertising, never make comparative-superiority claims about the practice, and always describe treatment outcomes as ranges dependent on candidacy, stage and adherence. The pharmacology content on finasteride and minoxidil needs particular care — describe evidence-based use, monitoring, and side-effect profiles honestly. Under-selling side effects erodes trust when patients experience them; over-emphasising side effects loses candidacy conversion.

Alopecia areata

The specialist vertical.
Auto-immune, evidence-heavy, JAK-inhibitor-era.

Alopecia areata (AA) is a distinct category — auto-immune, presenting as patchy or extensive hair loss, with a different demographic (paediatric and adult presentations both meaningful), a different clinical management (topical and intralesional corticosteroids, minoxidil, systemic corticosteroids, JAK inhibitors), and a different marketing surface. The AA patient — or parent — arrives at consultation with more emotional urgency than the AGA patient, and with meaningful clinical anxiety.

The JAK inhibitor category has expanded AA treatment options substantially since 2023-24. Ritlecitinib and baricitinib now have approved indications for severe alopecia areata in select markets and awareness in India has grown. A serious dermato-trichologist practice needs a compliance-safe JAK inhibitor category education page covering mechanism, current indications, monitoring requirements, and the cost picture. Frame as category-education, not brand-comparison.

The AA content stack: a hub page on alopecia areata (types, presentations, differential diagnosis versus AGA and telogen effluvium, treatment approach), a spoke on paediatric alopecia areata, a spoke on the JAK inhibitor category, a spoke on intralesional corticosteroid therapy, and a spoke on the psychological support dimension. Each page evidence-cited and named-authored.

Dermato-trichologist authority

How to position a medical scalp specialist.
The authority-content moves.

A dermato-trichologist is a dermatologist with focused sub-specialty practice in hair and scalp disorders. The title carries clinical weight but is unfamiliar to most patients — most first-time enquirers do not know the difference between "hair transplant surgeon" and "dermato-trichologist" and default to the surgical framing they have seen advertised. Positioning a practice as dermato-trichologist authority means clearly explaining what the sub-specialty means, why it matters for the researching patient, and where the surgical route enters (and does not enter) the picture.

The authority moves: a named-author byline on every content page with the dermato-trichologist credential explicit (MD Dermatology, additional training in trichology, years of practice); an "about the practice" page that explains the sub-specialty focus and includes the practice's diagnostic infrastructure (trichoscopy, scalp biopsy capability, hormonal-workup integration); a section on the site distinguishing medical alopecia from surgical hair transplant; and case-based content that shows the clinical thinking (never as promotional testimonial, always as educational case-discussion with appropriate anonymisation).

Trichoscopy content is a genuine differentiator. Few Indian dermatology practices publish trichoscopy educational content; the ones that do earn a clinical-authority signal that patients recognise even when they do not know the term. A hub page on "what a trichoscopy evaluation tells your dermatologist" with images of scalp micro-patterns (not patient identification) positions the practice as diagnostically rigorous rather than treatment-first.

PRP, minoxidil, finasteride

NMC-safe framing for prescription treatments.
The compliance craft.

PRP (platelet-rich plasma) has become one of the most-marketed procedural treatments in Indian medical alopecia. The category attracts both compliance-serious dermato-trichologist practices and aggressive-marketing operators that overstate outcomes. The compliance-safe PRP content frame: describe the procedure (blood draw, centrifugation, injection), the evidence-based indications (androgenetic alopecia primarily, adjunctive in some AA cases), the typical protocol (three to six sessions at monthly intervals, with maintenance), the cost-band range, and honest expectations described as "response varies with stage, candidacy and adherence" rather than as promises.

Minoxidil content: describe topical and oral formulations, the evidence base for AGA, the typical response timeline (three to six months to notice change), the shedding phenomenon in the first few weeks, the ongoing-use requirement to maintain benefit, and cost-band ranges. Never guarantee regrowth. Never publish before-and-after imagery as ad creative. The oral minoxidil category has expanded meaningfully in Indian practice since 2023 — a compliance-safe educational content piece on oral minoxidil is now a genuine authority move.

Finasteride content: describe the mechanism (5-alpha-reductase inhibition), the evidence base for male AGA, dosing, monitoring, and the side-effect profile honestly. The side-effect conversation on finasteride is complex — sexual side effects, mood effects and post-finasteride syndrome all exist in the literature at varying incidence estimates. Under-selling this content erodes patient trust when side effects present. Over-emphasising loses valid candidacy conversion. The compliance-safe frame is evidence-based and complete.

The referral bridge

Dermatology to hair transplant.
Sending only-when-appropriate patients.

The medical-first dermato-trichologist practice needs a referral relationship with a surgical hair transplant partner for the minority of patients who genuinely need FUE. The relationship is structural — a formal partnership rather than an ad-hoc suggestion. The compliant model: the patient consults the dermato-trichologist for medical evaluation, medical management stabilises the residual hair for 12 to 24 months where indicated, and where surgical candidacy is genuine the patient is referred to the surgical partner with a full clinical handoff.

The compliance frame: NMC prohibits per-referral fees. The compliant partnership is educational and clinical-infrastructure-led — the surgical partner accepts referred patients with clinical handoff, the dermato-trichologist accepts post-surgical medical-management referrals, and both parties maintain the patient's medical continuity. Never enter a fee-sharing arrangement.

The content architecture supports the bridge: publish a page on "when hair transplant becomes appropriate" that describes the Norwood stages where surgical consideration is genuine, the medical-management-first rationale, and the diagnostic checklist. Publish a page on "medical management after hair transplant" for patients returning to medical care after FUE. The two-way content architecture positions the dermato-trichologist practice as the responsible medical partner across the full hair-loss journey. See the hair transplant marketing agency pillar for the surgical side of the same conversation.

Frequently asked

About medical alopecia marketing
in India.

Separate positioning with a formal referral bridge works better than merged positioning. A dermato-trichologist practice positioning as medical-first attracts the early-stage androgenetic alopecia patient, the alopecia areata patient, the female pattern hair loss patient, and the paediatric alopecia patient — none of whom are the surgical hair transplant primary target. The referral bridge handles the minority who become surgical candidates. Merged positioning tends to dilute both funnels and produces a confused SERP presence.

Yes, if the content describes the procedure, evidence-based indications, typical protocol, cost-band range and outcomes as ranges dependent on candidacy. Never guarantee regrowth. Never publish before-and-after imagery as advertising. Never make comparative-superiority claims. The category attracts aggressive-marketing operators that overstate outcomes; a compliance-serious dermato-trichologist practice earns a differentiation signal by publishing evidence-based content that treats the patient as an adult who can weigh candidacy against realistic expectations.

Content depth on medical management is the differentiator. A surgical hair transplant practice will have heavy content on FUE, DHI, graft counts and technique variants; a dermato-trichologist can publish an equally deep content stack on androgenetic alopecia, alopecia areata, PRP, minoxidil, finasteride, JAK inhibitors and trichoscopy — none of which the surgical practice will match. On queries like 'dermato-trichologist [city]', 'androgenetic alopecia treatment', 'alopecia areata dermatologist', the depth-of-content practice consistently wins organic top-3 within six to nine months.

Yes, particularly with JAK inhibitor awareness growing. Search volume on 'alopecia areata,' 'JAK inhibitors for alopecia' and 'alopecia areata treatment' has grown 3 to 5 fold in the last 24 months. The category is smaller than androgenetic alopecia in absolute volume but carries higher enquiry-intent — an AA searcher is typically already diagnosed and looking for a specialist, whereas an AGA searcher is often at the early-awareness stage. AA enquiries convert to consult at 2 to 3 times the rate of comparable AGA enquiries.

ICG portfolio benchmark: Rs.480 to Rs.1,200 for medical alopecia in a metro. Male AGA sits at the lower end (Rs.480-Rs.750) driven by Meta Reels and Google Ads; female AGA at Rs.550-Rs.900; alopecia areata at Rs.700-Rs.1,200 with a lower ad-driven share and a higher search-and-YouTube driven share. Chronic-care LTV runs Rs.35,000 to Rs.90,000 per patient per year for compliant, retained treatment.

Within a Rs.60,000 to Rs.1,50,000 monthly Wave-1 budget: 30 to 40 per cent to Meta (Reels + boosted content, heavier on male AGA hooks), 25 to 35 per cent to Google Ads on high-intent AGA and AA queries, 20 to 25 per cent to content and SEO retainer for the hub-and-spoke build, 10 per cent to review-generation and GBP hygiene, 5 per cent to YouTube content production. The mix moves toward content and YouTube as the practice matures and the compounding organic base grows.

Yes. Oral minoxidil at low doses (0.25 to 5 mg daily) has expanded in Indian dermato-trichology practice since 2023 and awareness is growing. A compliance-safe educational hub on oral minoxidil for androgenetic alopecia — mechanism, dosing considerations, side-effect profile, monitoring, and comparison-to-topical framing — is now a genuine authority move. Frame as category-education, cite evidence carefully, and always describe outcomes as candidacy-dependent.

Yes. The compliant model is educational and clinical-infrastructure-led — the surgical partner accepts referred patients with clinical handoff, the dermato-trichologist accepts post-surgical medical-management referrals, and both parties maintain the patient's medical continuity. Never enter a per-referral fee-sharing arrangement — NMC prohibits this and the ethics-code exposure is real. The bridge should be documented in patient-communication content: 'when hair transplant becomes appropriate,' 'medical management after hair transplant' pages position the two practices as partners in the patient's overall hair-loss journey.

The ICG technology stack

Nine tools. One compounding system. HealthApex OS
Built in-house. Deployed in every engagement.

ICG's results are reproducible because they are built on proprietary infrastructure — not agency intuition or generic tools. These nine HealthApex OS platforms are what power every ICG engagement.

Healthcare CRM

Nexus CRM

Healthcare CRM & Lead Management

ICG's healthcare-specific CRM and lead management system. Specialty-configured funnel stages for IVF, dental, aesthetic, ortho, hospital OPD. 1-click CAPI + GCLID via Beacon. Hawk intelligence built in. DPDP-compliant by architecture. Deployed across 300+ healthcare centres.

  • Specialty-specific funnel stages, not generic SaaS pipeline
  • 1-click CAPI + GCLID via Beacon attribution
  • Telecaller leaderboard + adherence scoring native
  • DPDP Act 2023 compliant by architecture
Explore Nexus CRM →
Business Layer

Hawk

CRM Intelligence & Lead-Ops MIS

Sits as the business intelligence layer above your CRM — Nexus, Salesforce, LeadSquared, HubSpot, Zoho, or any custom CRM. Shows where leads are leaking, which effort is wasted, and which good leads were quietly downgraded by automation — not by a human decision.

  • Sits above your existing LMS — no replacement
  • 83% of effort goes to dead leads — surfaced Day 1
  • ~75% qualified-lead downgrades by automation
  • Free Lead-Leak Audit in 48 hours
Explore Hawk + free audit →
Attribution Core

Beacon

Attribution Engine & CAPI Middleware

Sits at the centre of every ICG attribution architecture. CAPI middleware connecting Meta Ads, Google Ads, WhatsApp and IVR to your CRM. Lifts Event Match Quality from 2.5 to 6+, reducing CPM 30–40% from the same budget.

  • Server-side CAPI — bypasses iOS privacy changes
  • EMQ 2.5 → 6+ across portfolio
  • 30–40% CPM reduction from EMQ lift alone
  • Multi-touch: ad → consultation → revenue
Explore Beacon →
Practice Management

HealthPro 360

PMS with built-in revenue intelligence layer

The only PMS that tracks cross-sell and up-sell opportunities within your existing patient base. 12 modules covering OPD, IPD, Pharmacy, Labs, Billing, Inventory, Patient Portal, Smart Scheduling, RBAC, AES-256 encrypted storage.

  • Only PMS with built-in Revenue Intelligence
  • Cross-sell signal tracking within existing patients
  • 12 modules: OPD, IPD, Pharmacy, Labs, Billing+
  • Audit trails + RBAC + AES-256 encryption
Explore HealthPro 360 →
Revenue Layer

Phoenix

Revenue intelligence built over your existing PMS

If you already have a PMS — Akhil Systems, Practo, or any other — Phoenix builds the business intelligence layer on top of it without replacement. Currently live across 46 centres for a national chain.

  • Works over your existing PMS — no migration
  • Daily action queue: Prevent Loss / Maintain / Grow
  • Catches unbilled services, collection gaps, lapsing patients
  • CPQL variance ₹620–₹3,800 → ₹680–₹1,420
Explore Phoenix →
YouTube Intelligence

YODA

YouTube analytics that measures patients, not views

The only YouTube intelligence platform built for healthcare business outcomes. Connects video performance to actual consultation bookings — not views, not subscribers. Patient testimonial videos generate 6.9× more consultations per view than condition explainers.

  • Consultation attribution per video — not views
  • Demand-gap: what patients search that your channel misses
  • 50+ doctor channels tracked across India
  • AIO readiness scoring: which videos AI tools cite
Explore YODA →
Governance & Transparency

Agency OS

Full transparency. Instant diagnosis. Zero surprises.

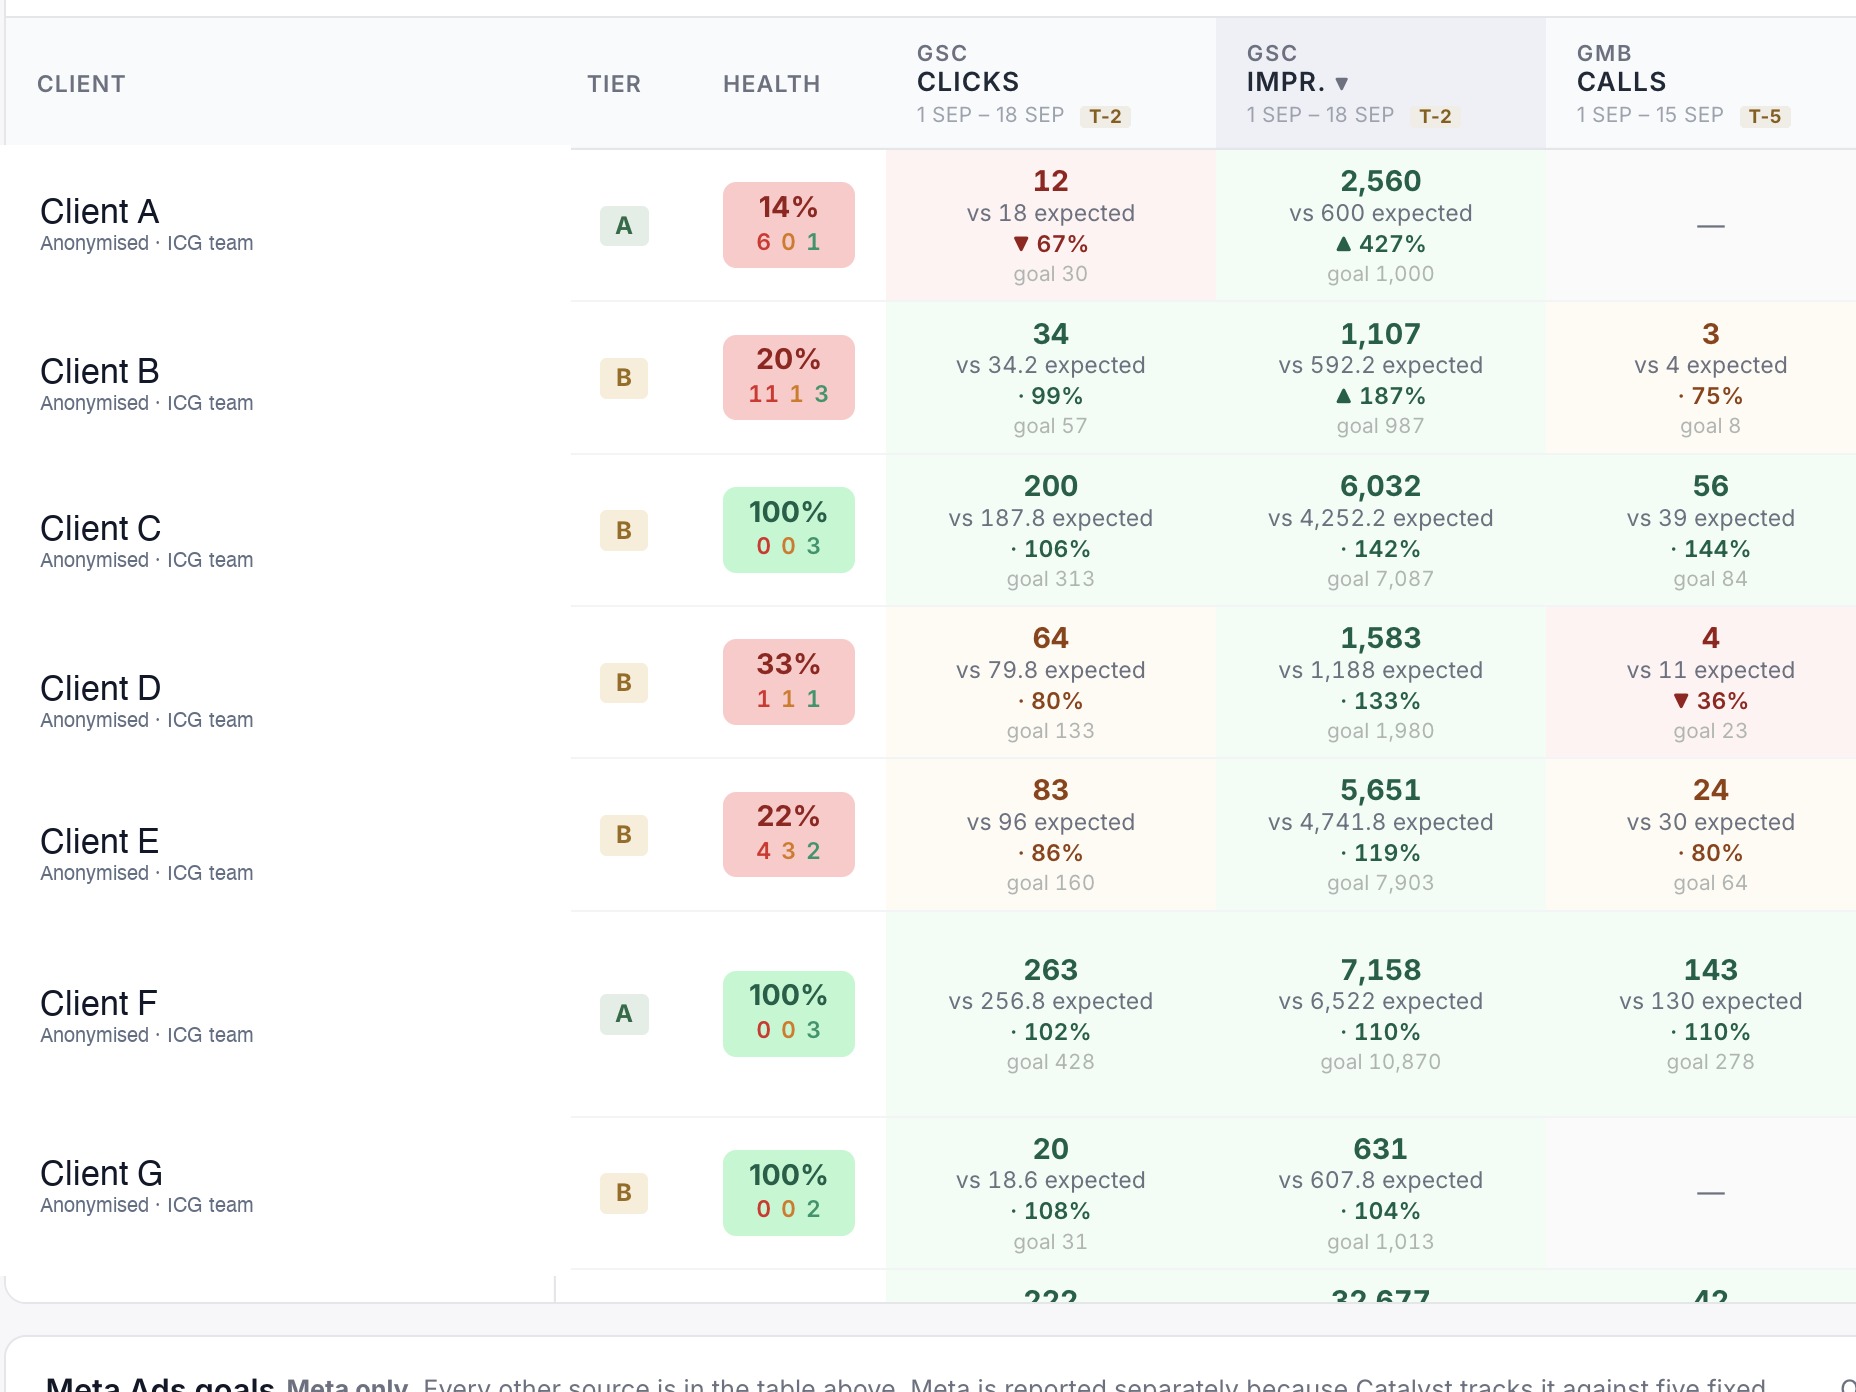
ICG's centralised governance platform — every client sees everything in real time, and ICG's team sees every problem the moment it surfaces. 30+ real-time alert systems fire the moment a metric drifts outside its performance envelope.

  • GSC, GA4, Google Ads, Meta Ads, IVR — one live view
  • 30+ real-time alert systems per account
  • CPQL drift alert at >15% week-on-week change
  • Client login: full transparency on your account
Explore Agency OS →
AEO & LLM Intelligence

AIO Intel

AI Overview + LLM citation tracking, healthcare-tuned

Knows the moment ChatGPT, Perplexity, Google AI Overviews and Gemini cite your brand in patient answers — and which content drove the citation. Bot-aware dashboard with GA4-registered custom dims (AIO source, AIO referrer) and IndexNow + GSC API integration.

  • Live tracking across ChatGPT / Perplexity / Google AIO / Gemini
  • Bot-aware: knows human vs scraper traffic
  • Custom GA4 dims register AIO source + referrer
  • IndexNow + GSC API: content surfaced to LLMs within hours
View AIO Intel dashboard →
Competitor Intelligence

Prism Spy

Every Meta + Google ad your competitors run, watched daily

Tracks 75+ Indian healthcare brands, 2,150+ active ads, ₹50Cr+ aggregate ad spend visibility per month. Surfaces what's working, what's been killed, what offers are emerging. Powers every ICG Meta Ads brief, Performance Marketing diagnostic, and IVF / derm / dental specialty campaign with real competitive intelligence.

  • 75+ brands tracked across 30+ healthcare specialties
  • 2,150+ active ads · daily refresh
  • Activity Feed: every spend / hook / pause logged
  • Offers Intelligence: 250+ offers in market tracked
Explore Prism Spy →
GBP Intelligence Platform

Angryturtle

Every Google Business Profile scored, tracked, protected, and grown from one command centre

ICG's proprietary Google Business Profile intelligence platform. Scores every listing across 7 dimensions, tracks rank on a live geo-grid across your actual service area, audits NAP + citations, monitors 531 suspension-risk factors continuously, and drafts Google Posts on cadence. Currently managing 143 healthcare listings with 0 suspensions and 4.76★ portfolio average across 28,137 reviews.

  • 143 listings under management · 0 suspensions · 4.76★
  • 7-dimension Health Score + 5-factor Rank OS per listing
  • Geo-grid rank tracking + NAP + Citation audit + Profile Shield
  • NMC + NABH + ART Act + DPDP compliance built into every content + review workflow
Explore Angryturtle →

Every ICG engagement runs on some combination of these ten HealthApex OS tools. The diagnostic determines which combination is right for your practice.

Explore HealthApex OS → See the full stack live on your account — free 30-min audit
The team behind your account

Every diagnostic is led by a founder.
You'll know their names before the engagement begins.

ICG was built by three IIT BHU engineers who entered healthcare marketing with a specific intent: to build the tools that didn't exist and run the campaigns that most agencies couldn't. When you book a diagnostic, Rohit or Abhash leads it personally. Not an account manager. Not a senior executive. The people who built what you're evaluating.

The ICG team — 60+ healthcare marketing specialists at Gurgaon HQ

60+ specialists.
One growth engine.

Performance marketers, analysts, AI engineers, content strategists, and operations specialists — all healthcare-only. Headquartered in Gurgaon since 2018.

Rohit Gupta — Leader, ICG

Rohit Gupta

Business & Growth Lead & Director

IIT BHU · IIM Rohtak

Rohit's first question in every diagnostic: "When you ask your agency why patients aren't booking — what do they say?" He says the answer tells him more than any dashboard.

Full profile →
Abhash Kumar — Leader, ICG

Abhash Kumar

Strategy & Analytics Lead & Director

IIT BHU · IIM Bangalore

Abhash built Beacon because most agencies couldn't answer one question: "Which of my campaigns generated that consultation?" He decided the problem was solvable in code. It was.

Full profile →
Deep Das — Leader, ICG

Deep Das

Technology & AI Lead & Director

IIT BHU

Deep built the 4-Bot patient lifecycle system after watching a client lose 60+ qualified leads in one week to a 6-hour WhatsApp response window. He decided the problem was solvable in code. It was.

Full profile →

Ready to build a
dermato-trichology practice engine?

Start with a complimentary 30-minute Alopecia Marketing Diagnostic from ICG. For medical dermato-trichologists positioning as the medical-first alternative to surgical hair transplant. Sibling reads: dermatology pillar, hair transplant marketing, psoriasis marketing.

Chat with a Co-Founder
🎯 Goal-linked · Fixed + Goal-based Variable Pay · 19-mo retention
Chat with a Co-Founder